Optimal asthma management focuses on controlling symptoms and preventing exacerbations. While serum and sputum eosinophil counts have traditionally been used to gauge eosinophilic airway inflammation, these measures are invasive and may not always be practical. The fraction of exhaled nitric oxide (FeNO) has emerged as a promising, non-invasive biomarker that reflects airway eosinophilia and may guide timely adjustments in inhaled corticosteroid therapy, particularly in patients with uncontrolled asthma. However, studies examining the relationship between FeNO, other inflammatory markers, and lung function remain limited, especially in sub-Saharan Africa, where FeNO testing is uncommon. This study aimed to investigate how FeNO levels relate to serum eosinophils, spirometry results, and asthma symptom control. This observational study was conducted at the asthma clinic of a tertiary care hospital and included 82 patients with physician-confirmed asthma receiving routine care. Each participant completed the asthma control test (ACT), underwent FeNO measurement and spirometry according to ATS guidelines, and provided blood samples for serum eosinophil counts. Correlation analyses assessed associations between FeNO, ACT scores, serum eosinophils, and spirometry metrics. Logistic regression was used to evaluate the relationship between elevated FeNO (> 50 ppb) and abnormal FEV1 percentage predicted (< 80%), controlling for age, sex, and BMI. Among the study population, females represented 72%, and 40.2% were aged 60 years or older. The median FeNO was 42.0 (26.0–52.5) ppb, the median ACT score was 20.0 (18–23), and the median serum eosinophil count was 0.25 (0.90–0.38) × 10⁹/L. Patients with partially or poorly controlled asthma had notably higher FeNO levels compared to those with well-controlled disease (P < 0.001). Overall, 57% of participants had well-controlled asthma, while 42% were uncontrolled. FeNO correlated positively with serum eosinophil counts (r = 0.450, P < 0.001) and negatively with ACT scores (r = −0.648, P < 0.001) and FEV1 percentage predicted (r = −0.353, P = 0.001). High FeNO levels were associated with over five times greater odds of having an abnormal FEV1 percentage predicted. In this cohort of asthma patients receiving inhaled corticosteroids, FeNO levels closely reflected airway eosinophilia, symptom control, and lung function. Elevated FeNO was strongly linked to impaired FEV1, suggesting that routine point-of-care FeNO testing, combined with ACT assessment, could serve as an effective strategy to improve asthma management and enhance disease control.
Background
Asthma is a widespread chronic inflammatory condition of the airways, exhibiting diverse phenotypes and manifesting as recurrent episodes of wheezing, breathlessness, chest tightness, and coughing [1]. Globally, more than 339 million people live with asthma, leading to roughly 250,000 deaths each year [2]. Mortality is disproportionately high in low- and lower-middle-income countries, highlighting significant gaps in asthma control in these settings [2, 3]. Asthma also imposes a substantial burden on global health, with an age-standardized DALYs rate of 273 per 100,000 [4, 5]. Therefore, improving disease control is essential to reduce both morbidity and mortality, though current management practices often fall short, resulting in increased healthcare utilization and compromised patient well-being [5–7].
Eosinophilic airway inflammation, driven by a TH2-type immune response to allergens, represents a central mechanism in many asthma patients [8, 9]. Elevated eosinophil levels in peripheral blood and bronchoalveolar lavage have been shown to correlate with asthma severity [9]. Corticosteroid therapy effectively targets this type of inflammation, leading to symptom relief and a substantial decrease—up to 60%—in acute exacerbations [10–12]. As a result, inhaled corticosteroids remain the cornerstone of asthma treatment worldwide [4, 13]. While spirometry and symptom-based tools such as the ACT are essential for assessing control, determining the degree of airway inflammation is crucial to guide appropriate therapy adjustments and improve outcomes, particularly in African populations.
Poorly controlled airway inflammation contributes to recurrent asthma attacks, frequent hospital and clinic visits, and greater reliance on short-acting bronchodilators. Identifying patients with eosinophilic inflammation is therefore critical to enable timely corticosteroid dose optimization and reduce disease burden [14, 15]. Serum and sputum eosinophil counts have traditionally served as biomarkers for airway inflammation and are considered modifiable risk factors in asthma care [15], often showing strong correlation with each other [9]. However, challenges, including difficulty in obtaining sputum and delayed test results, limit their clinical utility [16].
The recognition that nitric oxide levels rise in response to eosinophilic airway inflammation led to the development of FeNO testing as a non-invasive marker of airway inflammation [17, 18]. Elevated FeNO reflects worsening asthma control, whereas levels decline with corticosteroid therapy [18]. FeNO serves as an indirect indicator of airway hyper-responsiveness and eosinophilic inflammation and has been linked to disease severity, supporting its role in diagnosis and management [19, 20]. Although FeNO measurement is rapid, cost-effective, and feasible at the point of care, its correlation with traditional biomarkers and ACT scores has been inconsistent across studies [21–24].
In our setting, peripheral eosinophil count is currently the only available method for assessing airway inflammation; however, testing is costly and results are not always timely, which limits clinicians’ ability to adjust therapy promptly. Observed patterns of frequent exacerbations, heavy reliance on short-acting bronchodilators, limited ICS use, and a national age-adjusted mortality of 13.95/100,000 suggest suboptimal asthma control. FeNO measurement could offer a rapid, accessible, and affordable tool to guide treatment in resource-limited environments.
Given the scarcity of data from sub-Saharan Africa, this study aimed to investigate the relationship between FeNO and serum eosinophils in local asthma patients to determine its potential utility for routine clinical management.
Materials and Methods
Study design and measurements
This study employed a cross-sectional design and was conducted in the outpatient asthma clinic of a major tertiary hospital, the largest in the country. The facility receives patient referrals from district and regional hospitals, as well as from neighboring countries within the sub-region. The asthma clinic is managed by respiratory specialists and medical residents, seeing roughly 20–25 referred patients each month.
Participants included adults aged 18 years and above with a confirmed diagnosis of asthma. Eligible individuals were those who had attended the clinic for at least six months, were receiving inhaled corticosteroid therapy, and provided written informed consent. A systematic sampling strategy was utilized: the first patient on the clinic’s appointment list was selected, followed by every third patient thereafter. When a patient declined participation, the following individual on the list was invited instead.
Patients were excluded if they had chronic respiratory conditions other than asthma, experienced an acute exacerbation within 72 hours before the study, or had an acute upper or lower respiratory infection within two weeks before enrollment [25]. Additionally, individuals with coronary artery disease, congestive heart failure, cor pulmonale, or who were pregnant were not included.
A structured questionnaire captured demographic and clinical information, including treatment regimens and dosages, ACT questionnaire scores, and smoking history. Weight and height were measured using a SECA 877 scale and SECA 217 stadiometer, respectively, and body mass index (BMI) was calculated in kg/m². Venous blood samples were drawn into EDTA tubes for serum eosinophil analysis, which was performed within two hours using the XS-500i Sysmex hematology analyzer.
Spirometry testing
Spirometry was performed by trained technicians following the ATS guidelines [26] using a Vitalograph device. Testing occurred after blood collection and FeNO measurement. The highest recorded values of FEV₁, FVC, and the FEV₁/FVC ratio were considered. The device calculated predicted values for each index based on age, sex, height, and ethnicity [26]. An FEV₁ below 80% of the expected value was classified as abnormal.
Fraction of Exhaled Nitric Oxide (FeNO)
FeNO was assessed according to ATS guidelines [27] using the NO Breath analyzer (Bedfont Scientific Ltd., Maidstone, UK), which measures nitric oxide levels in parts per billion via electrochemical sensors. Each participant underwent three consecutive measurements, and the mean value was recorded. To minimize the influence of dietary and lifestyle factors, participants avoided nitrate-rich vegetables (e.g., lettuce and spinach), coffee for two hours, and alcohol for 12 hours before testing; some participants were asked to return the next day to ensure compliance. FeNO levels were categorized as low (< 25 ppb), intermediate (25–50 ppb), or high (> 50 ppb) following ATS recommendations [27].
Asthma control test
Asthma symptoms over the preceding four weeks were evaluated using the asthma control test (ACT) questionnaire. Patients provided self-reported ratings for items including limitations in daily activities, shortness of breath, nighttime awakenings, use of rescue medication, and overall perception of asthma control [28].
ACT scores range from five to 25, with scores of 20–25 indicating well-controlled asthma, 16–19 reflecting partially controlled asthma, and 5–15 representing poorly controlled asthma.
Statistical analysis
All analyses were performed using SPSS version 25 software (SPSS, Chicago, IL). Data with a normal distribution are expressed as mean ± standard deviation, whereas non-normally distributed data are presented as median with interquartile ranges. Chi-square tests were applied to assess associations between categorical variables. For comparison of means across the three FeNO groups (low, intermediate, high), one-way analysis of variance (ANOVA) was employed, followed by Tukey’s post hoc test. Differences in medians among more than two groups were analyzed using the Kruskal–Wallis test. Spearman’s rank correlation coefficient was used to evaluate relationships between continuous variables. Logistic regression was conducted to explore the association between FeNO levels and an abnormal FEV₁ percentage predicted (FEV₁ < 80% of predicted), adjusting for potential confounders, including age, sex, and BMI. A P-value < 0.05 was considered statistically significant.
Results
Participant characteristics
The study enrolled 82 adult patients with asthma. As summarized in Table 1, the mean age was 52.72 ± 13.52 years, with females comprising 72% of the cohort. Approximately 40% of participants were aged 60 years or older. The mean BMI was 28.87 ± 5.27 kg/m², and around 77% of participants were classified as overweight or obese. Only 5% of participants reported a history of current or former smoking. Childhood-onset asthma was reported by 15 participants (18%), whereas 39 (47.6%) and 28 (34.1%) reported onset during adolescence and adulthood, respectively. The duration of asthma was less than one year in 4 patients (4.9%), while the majority (72 patients, 87.8%) reported living with asthma for more than ten years.
|
Table 1. Clinical characteristics of the study participants based on ATS categorization of FeNO |
|||||
|
All subjects (n = 82) |
FeNO < 25 ppb (n = 19) |
FeNO 25–50 ppb (n = 38) |
FeNO > 50 ppb (n = 25) |
P-value |
|
|
Age (years, mean ± SD) |
52.72 ± 13.52 |
53.47 ± 15.69 |
55.68 ± 11.54 |
47.64 ± 13.52 |
0.065 |
|
Age group in years (mean (SD)) |
|||||
|
19–29 |
6 (7.3) |
2 (10.5) |
1 (2.6) |
3 (12.0) |
0.474 |
|
30–39 |
8 (9.8) |
2 (10.5) |
3 (7.9) |
3 (12.0) |
|
|
40–49 |
15 (18.3) |
3 (15.8) |
5 (13.2) |
7 (28.0) |
|
|
50–59 |
20 (24.4) |
3 (15.8) |
11 (28.9) |
6 (24.0) |
|
|
≥ 60 |
33 (40.2) |
9 (47.4) |
18 (47.4) |
6 (24.0) |
|
|
Gender (mean (SD)) |
|||||
|
Male (%) |
23 (28) |
9 (47.4) |
8 (21.1) |
6 (24.0) |
0.098 |
|
Female (%) |
59 (72) |
10 (52.6) |
30 (78.9) |
19 (76.0) |
|
|
BMI category (mean (SD)) |
|||||
|
18.50–24.99 kg/m2 |
19 (23.2) |
3 (15.8) |
9 (23.7) |
7 (28.0) |
0.390 |
|
25.00–29.99 kg/m2 |
34 (41.5) |
8 (42.1) |
19 (50.0) |
7 (28.0) |
|
|
≥ 30.00 kg/m2 |
29 (35.4) |
8 (42.1) |
10 (26.3) |
11 (44.0) |
|
|
Asthma treatment (ICS) (mean (SD)) |
|||||
|
Beclomethasone |
5 (6.1) |
2 (10.5) |
3 (7.9) |
0 (0.0) |
0.243 |
|
Formeterol + bedesonide |
25 (30.5) |
6 (31.6) |
8 (21.1) |
11 (44.0) |
|
|
Salmeterol + fluticasone |
50 (61.0) |
10 (52.6) |
27 (71.1) |
13 (52.0) |
|
|
Salmeterol + fluticasone + montelucast |
2 (2.4) |
1 (5.3) |
0 (0.0) |
1 (4.0) |
|
|
Asthma control using the ACT score (mean (SD)) |
|||||
|
Well controlled |
47 (57.3) |
18 (94.7) |
27 (71.1) |
2 (8.0) |
< 0.001 |
|
Partially controlled |
19 (23.2) |
0 (0.0) |
7 (18.4) |
12 (48.0) |
|
|
Very poorly controlled |
16 (19.5) |
1 (5.3) |
4 (10.5) |
11 (44.0) |
|
Data are presented as counts with percentages, medians with interquartile ranges, or means ± standard deviations. Abbreviations used include BMI for body mass index and FeNO for fraction of exhaled nitric oxide.
The median ACT score among participants was 20.0 (IQR: 18–23). According to Table 1, 47 patients (57%) had well-controlled asthma, while 35 patients (42%) were classified as having uncontrolled asthma. All participants were receiving inhaled corticosteroid therapy, with the majority using combination inhalers, predominantly Salmeterol/Fluticasone formulations.
Analysis of FeNO levels revealed a median value of 42.00 (26.00–52.50) ppb. As shown in Table 1, 63 patients (77%) had intermediate to high FeNO levels. There was a statistically significant relationship between FeNO levels and asthma control as determined by ACT scores (P < 0.001). The type of asthma treatment also showed a notable, though not statistically significant, association with FeNO values (P = 0.243). Blood eosinophil counts varied according to asthma control status, with median values of 0.17 (0.07–0.36) × 10⁹/L in well-controlled patients, 0.28 (0.12–0.39) × 10⁹/L in partially controlled patients, and 0.30 (0.12–0.39) × 10⁹/L in poorly controlled patients (P < 0.001).
Association between Serum Eosinophils, FeNO, and Spirometry
As indicated in Table 2, the mean serum eosinophil count was 0.25 (0.90–0.38) × 10⁹/L, while the mean FEV₁ percentage predicted was 68.34 ± 23.92%. A strong association was found between serum eosinophil levels and FeNO measurements (P < 0.001). Furthermore, FEV₁% predicted was significantly correlated with FeNO values (P = 0.010).
|
Table 2. Blood eosinophils and spirometry results |
|||||
|
All subjects (n = 82) |
FeNO < 25ppb (n = 19) |
FeNO 25–50 ppb (n = 38) |
FeNO > 50 ppb (n = 25) |
P-value |
|
|
Serum eosinophil count, 109/L |
0.25 (0.09–0.38) |
0.08 (0.05–0.13) |
0.26 (0.13–0.38) |
0.37 (0.21–0.40) |
< 0.001 |
|
FEV1% predicted |
68.34 ± 23.92 |
79.58 ± 27.32 |
69.45 ± 21.96 |
58.11 ± 20.41 |
0.010 |
|
FVC% predicted |
82.90 ± 16.74 |
86.17 ± 16.40 |
81.71 ± 16.47 |
82.23 ± 17.72 |
0.625 |
|
FEV1/FVC ratio |
0.64 ± 0.15 |
0.66 ± 0.12 |
0.67 ± 0.16 |
0.64 ± 0.15 |
0.038 |
Data are summarized as frequencies with percentages, medians with interquartile ranges, or as means ± standard deviations. Abbreviations: FVC = forced vital capacity; FEV₁ = forced expiratory volume in one second.
FeNO Levels in Relation to ACT Categories
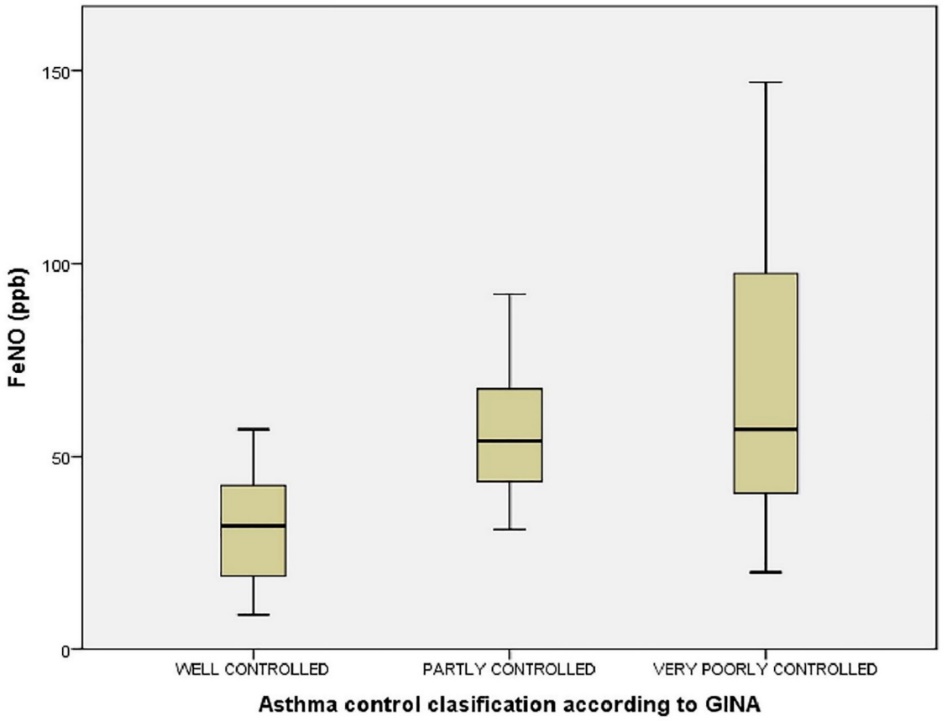
Median FeNO concentrations were markedly elevated among participants with partly controlled and very poorly controlled asthma compared to those with well-controlled disease (P < 0.001). Specifically, the median FeNO values were 32 ppb (IQR: 19–42.5) in the well-controlled group, 54 ppb (IQR: 43.5–67.5) in the partly controlled group, and 57 ppb (IQR: 40.5–97.5) in the very poorly controlled group. Post hoc analysis revealed no statistically significant difference between the partly controlled and very poorly controlled categories (P = 1.00) (Figure 1).
|
|
|
Figure 1. Fractional exhaled nitric oxide (FeNO) concentrations in patients stratified by asthma control status using the GINA classification |
Association between Inflammatory Markers and ACT Scores
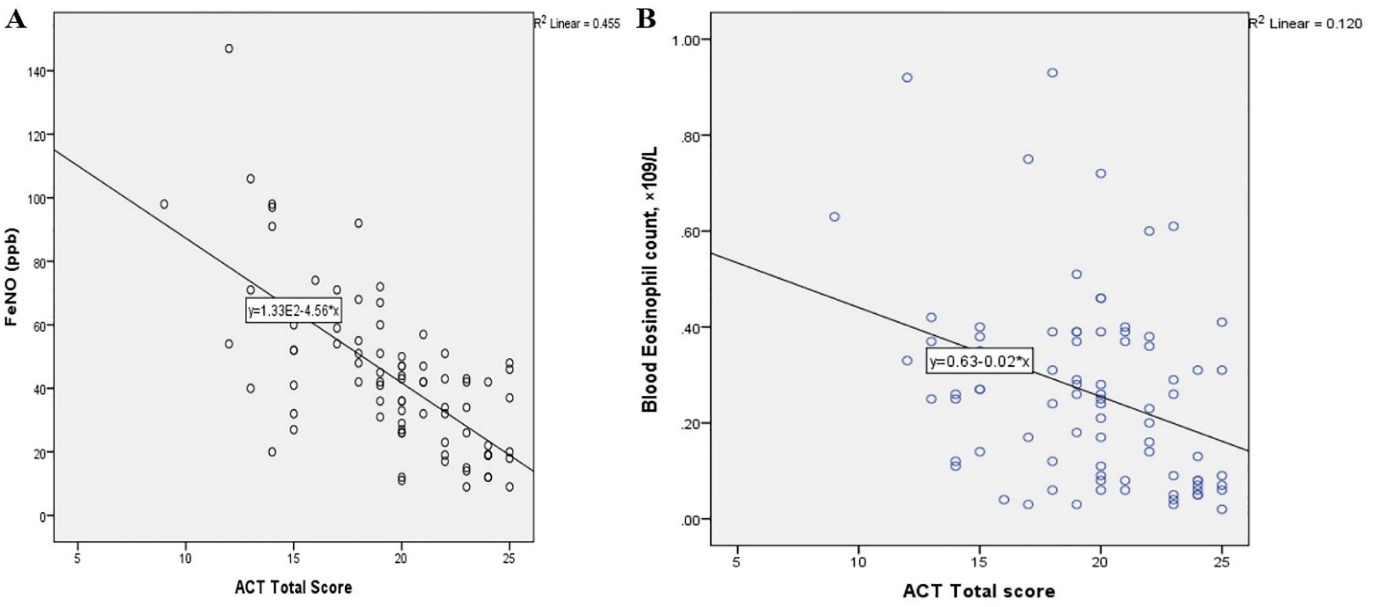
Analysis revealed a strong inverse relationship between FeNO levels and ACT scores among the study participants (r = –0.648, P < 0.001) (Figure 2A). Similarly, peripheral blood eosinophil counts were also negatively correlated with ACT scores, though the association was weaker (r = –0.339, P = 0.002) (Figure 2B).
|
|
|
Figure 2. (A) Scatterplot of fractional exhaled nitric oxide (FeNO) versus asthma control test (ACT) score. (B) Scatterplot of peripheral eosinophil counts versus ACT score |
Association of Inflammatory Indicators with FEV₁% Predicted
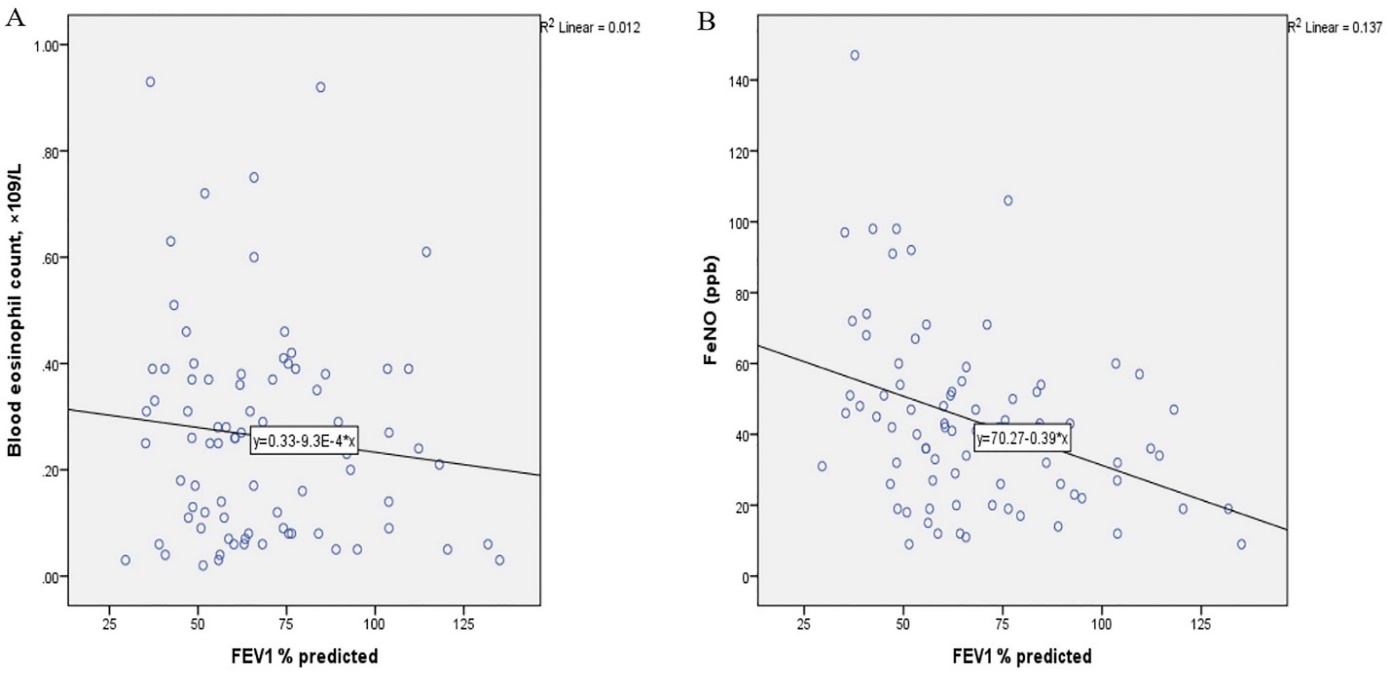
Analysis revealed that circulating eosinophil levels were not linked to FEV₁% predicted in this sample (r = –0.082, P = 0.462) (Figure 3A). In contrast, FeNO exhibited a clear inverse relationship with FEV₁% predicted, reaching statistical significance (r = –0.353, P = 0.001) (Figure 3B).
|
|
|
Figure 3. (A) Scatterplot illustrating the relationship between peripheral eosinophil count and FEV₁% predicted in patients with asthma. (B) Scatterplot showing the association between FeNO and FEV₁% predicted in asthma patients |
Link Between FeNO and Circulating Eosinophils in Ghanaian Asthma Patients
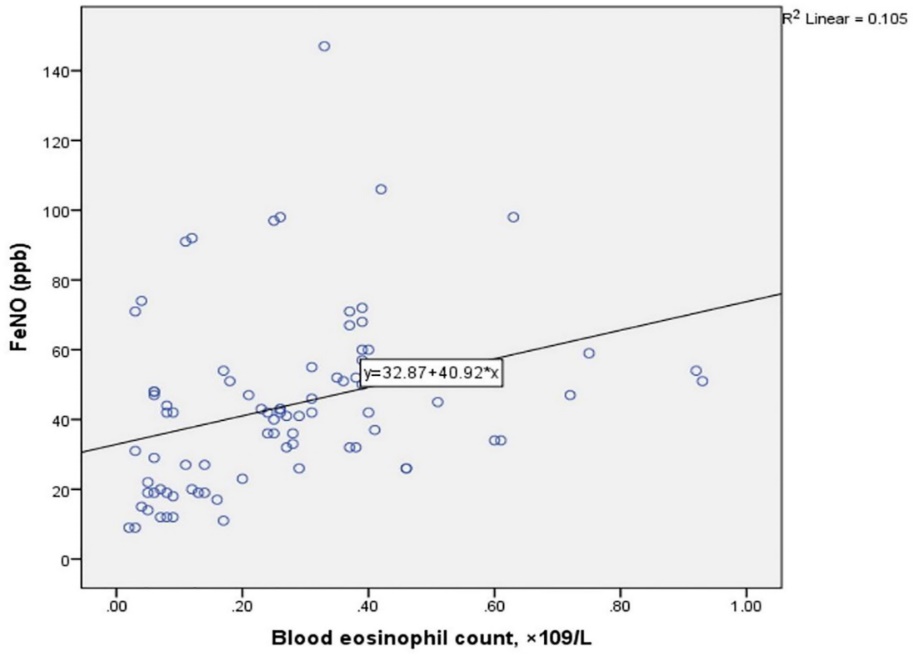
The correlation analysis indicated a moderate positive relationship between fractional exhaled nitric oxide and blood eosinophil concentration, which reached statistical significance (r = 0.450, P < 0.001) (Figure 4).
|
|
|
Figure 4. Scatterplot illustrating FeNO and blood eosinophil count in Ghanaians with asthma |
Logistic Regression Analysis of FeNO and Abnormal FEV1% Predicted in Ghanaian Asthma Patients
The logistic regression analysis demonstrated that elevated FeNO was strongly linked with reduced FEV1% predicted values. In the crude model, individuals presenting with FeNO concentrations greater than 50 ppb had nearly a fivefold likelihood of impaired lung function compared with those with FeNO levels below 25 ppb. After adjusting for confounders, this association remained robust, with high FeNO still conferring more than a fivefold increased probability of abnormal FEV1% predicted (model 2; Table 3).
|
Table 3. Logistic regression models abnormal FEV1 in Ghanaians with asthma |
|||
|
Odds ratio |
95% Confidence interval |
P-value |
|
|
Model 1 |
5.333 |
1.176–24.178 |
0.030* |
|
Model 2 |
5.104 |
1.024–25.442 |
0.047* |
Model 1 represents the unadjusted analysis (FeNO only), while Model 2 includes adjustments for age, sex, and body mass index (BMI).
*Statistical significance was set at P < 0.005; CI = confidence interval at the 95% level; BMI = body mass index.
Discussion
Persistent airway inflammation is a defining characteristic of bronchial asthma, leading to obstructed expiratory airflow and posing a potential risk of mortality if inadequately managed [1]. Approximately half of all asthma patients present with eosinophilic airway inflammation, and studies have demonstrated that reducing this inflammation through inhaled corticosteroid (ICS) therapy is linked to favorable clinical outcomes, including fewer daytime and nocturnal symptoms, reduced exacerbation frequency, and an overall improvement in quality of life [1]. For this reason, monitoring airway inflammation in asthma not only facilitates diagnosis and grading of disease severity but also provides valuable insight into therapeutic response, whether to corticosteroids or biologic agents in more severe cases [29].
Assessment of type 2 inflammation often relies on serum or sputum eosinophil counts, with sputum analysis considered the most accurate, though not routinely available in many settings [9, 10]. In 1993, researchers at the Karolinska Institute in Sweden first identified elevated nitric oxide levels in the exhaled breath of asthma patients compared with healthy controls [30]. Eosinophils, as a major effector cell population in the asthmatic airway, contribute to exhaled nitric oxide production through inducible nitric oxide synthase activity [30]. Subsequent research has consistently confirmed that fractional exhaled nitric oxide (FeNO) serves as a surrogate marker of eosinophilic airway infiltration [31–33]. Unlike invasive blood or sputum tests, FeNO offers a rapid, non-invasive, point-of-care measure that enables timely adjustment of ICS treatment, a role now emphasized in contemporary asthma management guidelines [34].
In addition to biological markers, patient-reported outcome measures provide critical information about disease control. Tools such as the asthma control test (ACT) are validated instruments that not only quantify disease status but also predict the likelihood of future exacerbations, reflecting poor control [35]. The ACT has proven responsive to changes in both symptoms and lung function [23]. Because asthma control is often evaluated through such symptom-based questionnaires, inflammatory markers like FeNO and eosinophil counts must demonstrate meaningful associations with ACT outcomes. In the present study, 43% of patients were classified as uncontrolled despite most being prescribed combination therapy with ICS and long-acting beta-agonists. It is plausible that actual rates of poor control could be higher, given that this study was conducted in a tertiary facility where patients may have better access to specialist care. Nonetheless, these findings align closely with previously reported control rates of 44.3% in South Africa and 44.4% in Uganda. They are slightly higher than the 30.9% reported in Nigeria in a systematic review of children aged 6–18 years [36, 37].
Our findings further demonstrated that both FeNO and serum eosinophil counts were inversely associated with ACT scores [23, 38]. Elevated FeNO levels corresponded with worsening asthma control and were shown to decline following corticosteroid therapy [18]. These results support the principle that effective suppression of eosinophilic airway inflammation should translate into improved symptom control and quality of life, a relationship confirmed in this study. Similarly, incorporation of FeNO monitoring into pediatric asthma care has been shown to significantly enhance ACT scores [39]. However, contrasting evidence exists; Szefler et al. [40] reported no significant effect of FeNO-guided monitoring on ACT outcomes among adolescents and adults with asthma [40].
Although both FeNO and serum eosinophils are recognized as reliable indicators of airway inflammation, they operate through distinct inflammatory pathways, which may account for the inconsistent or weak direct correlations reported in previous studies [41, 42]. The fraction of exhaled Nitric Oxide is regulated primarily by IL-14 and IL-13 (type 2 inflammation), whereas IL-5 drives peripheral eosinophilia. In our study, however, we observed a strong positive correlation between these two biomarkers (r = 0.450, P < 0.001). Gao et al. [33] demonstrated that FeNO and serum eosinophils independently and accurately predict sputum eosinophilia in patients with uncontrolled asthma, though no direct correlation between them was noted. Evidence suggests that concurrent elevations in both FeNO and serum eosinophil levels are more strongly linked to an increased risk of acute asthma events than elevations in either marker alone [32]. These findings indicate that combining FeNO measurements with serum eosinophil counts could enhance the prediction of future adverse outcomes in asthma patients.
Reduced FEV1, particularly values below 60% of predicted, has been identified as an independent risk factor for future adverse events in treated asthma patients and remains a key parameter in evaluating asthma control during clinic visits [2, 43]. The association between airway inflammation and FEV1 is not fully clarified, with studies reporting varying results [42, 44]. In our analysis, participants with an abnormal FEV1% predicted who also had elevated FeNO (> 50 ppb) faced a more than fivefold increased risk of abnormal FEV1 compared to those with low FeNO (< 25 ppb).
In our setting, long intervals between clinic visits and the costs associated with serum eosinophil testing pose significant challenges for routine monitoring of airway inflammation. Our findings underscore the utility of FeNO as a rapid, indirect biomarker for eosinophilic airway inflammation, offering a practical and cost-effective means to assess asthma control and facilitate timely ICS treatment adjustments.
Conclusions
Most patients with well-controlled asthma were found in the low FeNO group. FeNO showed significant correlations with ACT scores, serum eosinophil counts, and FEV1% predicted. These results suggest that incorporating FeNO assessment alongside ACT scores or standard care in asthma clinics may help further enhance asthma control rates.
Acknowledgments: None.
Conflict of interest: None.
Financial support: None.
Ethics statement: None.