This research explored the therapeutic outcomes of recombinant human granulocyte-macrophage colony-stimulating factor (rhGM-CSF) gel, medical collagen sponge, and their combined application for treating deep second-degree burns on the head, face, or neck in infants. A total of 108 infants suffering from deep second-degree burns in the head, face, or neck areas were randomly allocated to three groups: one receiving rhGM-CSF gel alone, one treated with medical collagen sponge alone, and a third group receiving both rhGM-CSF gel and medical collagen sponge. Clinical endpoints measured included time for scab detachment, wound healing duration, rate of bacterial infection, and Vancouver Scar Scale (VSS) scores.
Infants in the combination therapy group (rhGM-CSF + collagen sponge) experienced significantly faster scab detachment and wound closure than those receiving either rhGM-CSF alone or collagen sponge alone (P < .05). Additionally, the proportion of positive bacterial cultures was lowest in the combination group (P < .05). At the three-month follow-up, VSS evaluation—covering scar thickness, flexibility, pigmentation, and vascularity—showed markedly lower scores in the combination group compared with the single-treatment groups (P < .05). Administering rhGM-CSF gel together with medical collagen sponge significantly improves treatment outcomes for deep second-degree burns in infants’ head, face, and neck regions. This strategy accelerates scab removal and wound healing, lowers infection risk, and reduces scarring and pigmentation, supporting its broader clinical adoption.
Introduction
Burn injuries cause substantial mortality worldwide, with infants being particularly vulnerable due to inadequate supervision or low safety awareness. Globally, they rank as the fifth most common cause of nonfatal injuries in children [1]. Economic factors also influence burn prevalence, with higher rates in low- and middle-income countries [2]. In China, burns among infants are increasingly frequent, especially on the face and neck, where injuries are often severe, complicated, and associated with poor prognosis. Prompt, proper management is crucial for improved outcomes and reduced financial burden.
Granulocyte-macrophage colony-stimulating factor (GM-CSF) is a cytokine that regulates granulocytes and macrophages. While not essential for baseline myelopoiesis, GM-CSF is released by multiple cell types in response to injury or inflammation, stimulating neutrophil proliferation and monocyte differentiation, which supports tissue repair [3]. Experimental studies indicate that GM-CSF administration—locally or systemically—significantly shortens wound healing [4, 5]. Clinically, rhGM-CSF gel has been applied to burn patients, including pediatric cases, without significant adverse effects [6, 7], offering a safe and effective therapeutic option.
Medical collagen sponge, composed mainly of type I collagen, is biocompatible and well-tolerated by human tissue [8]. It is frequently used as an adjunctive material to promote wound healing [9]. However, its specific benefits in infant burn management remain unclear. This study compares the clinical outcomes of rhGM-CSF gel, medical collagen sponge, and their combination in treating deep second-degree burns of the head, face, or neck in infants.
Materials and Methods
Study population
From January 2020 to January 2022, 108 infants with deep second-degree burns located on the head, face, or neck were enrolled. Guardians were fully informed about the study, provided consent for participation, and signed written agreements. Permission for using burn images in this manuscript was obtained from guardians. This research was conducted in accordance with the Declaration of Helsinki and approved by the Ethics Committee of Wenzhou Medical District, NO.906 Hospital of Joint Logistics Support Force of PLA (906ECA-2020-001).
Eligibility criteria
Inclusion criteria:
Exclusion criteria:
Randomization and blinding
Participants were assigned randomly into three equal groups of 36 infants each: rhGM-CSF, medical collagen sponge, and rhGM-CSF + medical collagen sponge. A flow chart illustrates the enrollment process. There were no significant differences among groups regarding age, gender, or burn size (Table 1). Study staff recorded group assignments and treatment details. All patients were followed for 3 months post-healing.
|
Table 1. Baseline characteristics (χ̄±s) |
|||
|
Group |
Male/Female (n/n) |
Age (years) |
Wound area (% TBSA) |
|
rhGM-CSF group |
20/16 |
1.6 ± 0.7 |
6.28 ± 2.31 |
|
Medical collagen sponge group |
22/14 |
1.8 ± 0.5 |
7.00 ± 2.62 |
|
rhGM-CSF + medical collagen sponge group |
19/17 |
1.7 ± 0.4 |
6.67 ± 3.28 |
|
F value |
— |
7.00 |
1.20 |
|
P value |
.12 |
.31 |
.54 |
Note: rhGM-CSF = recombinant human granulocyte-macrophage colony-stimulating factor
Treatment procedures
All patients received standard hospital care. Large blisters were drained, while smaller blisters were preserved. Wounds were cleaned using benzalkonium chloride solution, rinsed with saline, and exposed to infrared therapy. Intravenous administration of glucose, vitamin C, and latamoxef sodium was provided to maintain hydration, reduce oxidative stress, and prevent infection.
All wounds were dressed with sterile vaseline gauze. Treatments were performed by trained clinical staff.
Outcome measures
Efficacy was evaluated based on: scab detachment time, wound healing time, bacterial positivity rate, and Vancouver Scar Scale (VSS) scores.
Scab detachment time
Defined as the day when wounds were observed to be free of scabs after treatment.
Wound healing time
Defined as the day when wounds achieved complete closure.
Bacterial positivity rate
After 7 days of treatment, wound exudates were collected and cultured to detect microbial growth.
Vancouver scar scale (VSS)
VSS was used to assess scar quality post-healing, including parameters of thickness, pliability, pigmentation, and vascularity [10].
Statistical analysis
Data were analyzed using SPSS 25.0 (IBM, USA). Selection of the t-test, Mann–Whitney test, or Chi-square test depended on the distribution and variance homogeneity. Statistical significance was set at P < .05.
Results and Discussion
Scab detachment duration
Table 2 displays the average duration for scab detachment among the three groups. Infants treated with rhGM-CSF alone had a mean detachment time of (8.45 ± 2.52) days, which was shorter than that observed in the medical collagen sponge group. The combination of rhGM-CSF with medical collagen sponge yielded the fastest scab resolution, outperforming both individual treatments.
|
Table 2. Mean scab detachment and wound healing times (χ̄± s) |
|||
|
Group |
Number of cases |
Scab dissolution time (days) |
Wound healing time (days) |
|
rhGM-CSF group |
36 |
8.45 ± 2.52 |
19.63 ± 2.65 |
|
Medical collagen sponge group |
36 |
9.68 ± 2.28* |
18.25 ± 3.21* |
|
rhGM-CSF + medical collagen sponge group |
36 |
6.88 ± 1.73*,† |
15.73 ± 2.47*,† |
|
F value |
— |
14.628 |
18.029 |
|
P value |
— |
< .01 |
< .01 |
rhGM-CSF = recombinant human granulocyte-macrophage colony-stimulating factor.
*Significant difference versus rhGM-CSF group, P < .05.
†Significant difference versus collagen sponge group, P < .05.
Duration of wound healing
The mean time for complete wound closure was (19.63 ± 2.65) days in the rhGM-CSF group, (18.25 ± 3.21) days in the collagen sponge group, and (15.73 ± 2.47) days in the combination therapy group (Table 2). These findings indicate that applying rhGM-CSF together with medical collagen sponge substantially shortens the overall healing period compared to either treatment alone.
Incidence of bacterial positivity
After seven days, bacterial culture results demonstrated that the combination group had the fewest positive cases (F = 31.24, P = .03) (Table 3). The rhGM-CSF-only group also showed a lower incidence of bacterial positivity than the collagen sponge group, suggesting better infection control.
|
Table 3. Bacterial-positive and -negative case distribution across groups |
|
|
Grouping |
Positive cases/negative case |
|
rhGM-CSF group |
7/29 |
|
medical collagen sponge group |
10/26 |
|
rhGM-CSF + medical collagen sponge group |
3/33 |
|
F |
31.24 |
|
P value |
.03 |
rhGM-CSF = recombinant human granulocyte-macrophage colony-stimulating factor.
Scar quality assessment (VSS)
At three months post-treatment, VSS scores were assessed. In the rhGM-CSF group, pigmentation scores were lower than in the collagen sponge group, while pliability and vascularity scores were higher (Table 4). The combination therapy group had higher scores for pigmentation, thickness, pliability, and vascularity compared with either monotherapy group. Consequently, the overall VSS total score was greatest in the combination group, indicating superior scar outcomes.
|
Table 4. Vancouver Scar Scale comparison (χ̄± s) |
||||||
|
Group |
Number of cases |
Pigmentation |
Height |
Pliability |
Vascularity |
Total VSS score |
|
rhGM-CSF group |
36 |
1.38 ± 0.18 |
1.55 ± 0.24 |
1.64 ± ± 0.25 |
2.01 ± 0.18 |
7.16 ± 1.61 |
|
Medical collagen sponge group |
36 |
1.49 ± 0.24* |
1.52 ± 0.13 |
1.35 ± 0.32* |
1.56 ± 0.22* |
6.22 ± 1.92* |
|
rhGM-CSF + medical collagen sponge group |
36 |
1.13 ± 0.06*,† |
1.14 ± 0.18*,† |
0.95 ± 0.13*,† |
1.32 ± 0.37*,† |
4.93 ± 1.56*,† |
|
F value |
— |
39.27 |
52.77 |
152.41 |
60.87 |
15.54 |
|
P value |
— |
< .001 |
< .01 |
< .01 |
< .01 |
< .01 |
rhGM-CSF = recombinant human granulocyte-macrophage colony-stimulating factor; VSS = Vancouver Scar Scale.
*Significant difference versus rhGM-CSF group, P < .05.
†Significant difference versus collagen sponge group, P < .05.
Case illustration
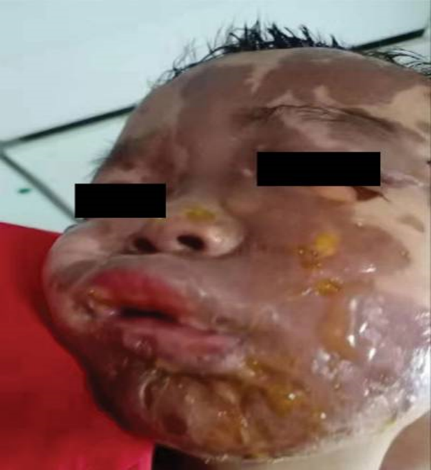
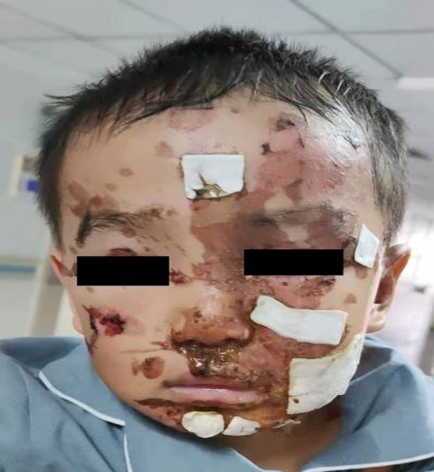
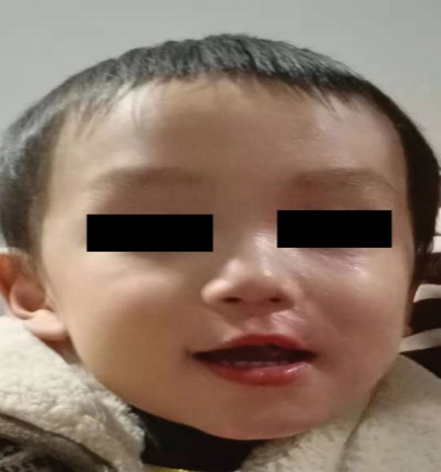
A representative case involved a 2-year-old infant with scald burns covering the face and neck, affecting approximately 4% of total body surface area (Figure 1). Physical examination revealed swelling, scattered blisters, intact epidermis, and reduced pain sensation. The treatment protocol included intravenous glucose, vitamin C, and latamoxef sodium to support hydration, antioxidant activity, and infection prevention, alongside infrared therapy. The wound was treated with rhGM-CSF gel, followed by gentle coverage with a saline-soaked collagen sponge. By day 7, the wound showed notable improvement (Figure 2), and complete healing was achieved by day 15, allowing for hospital discharge. Follow-up indicated satisfactory recovery without visible scars (Figure 3).
|
|
|
Figure 1. Burn injury on the face and neck at admission. |
|
|
|
Figure 2. Wound appearance after 7 days of combination treatment. |
|
|
|
Figure 3. Final follow-up outcome post-treatment. |
Wounds frequently occur in daily life due to various internal or external causes, among which burn injuries are particularly complex and prone to infection and excessive scar formation [11]. Children represent nearly half of all burn patients [12]. Although pediatric skin generally exhibits strong regenerative capacity, its immature development and an underdeveloped immune system make infants more susceptible to infections, which can result in deeper and more severe injuries. Limited cooperation during medical care further complicates management. Therefore, early interventions targeting infection control and inflammation reduction are critical for accelerating wound repair and improving scar outcomes.
In China, three growth factors are commonly used topically for wound management: recombinant human granulocyte-macrophage colony-stimulating factor (rhGM-CSF), epidermal growth factor (EGF), and fibroblast growth factor (FGF). Mechanistically, rhGM-CSF primarily regulates neutrophils and macrophages during the inflammatory phase, initiating the repair process and contributing throughout the wound healing stages. In contrast, EGF and FGF mainly act during the proliferation phase, which follows inflammation. Previous studies indicate that rhGM-CSF achieves better outcomes than EGF or FGF. A recent network meta-analysis demonstrated that rhGM-CSF more effectively shortens burn wound healing times compared with EGF and FGF [13]. This evidence guided our selection of rhGM-CSF in this study.
As a colony-stimulating factor, GM-CSF has pleiotropic effects, promoting expansion and differentiation of myeloid progenitor cells, particularly in cases of myelotoxicity or myelosuppression caused by chemotherapy or radiotherapy [14, 15]. Beyond hematopoietic regulation, GM-CSF also supports wound healing [16], reduces sepsis [17], and improves pulmonary function in autoimmune pulmonary alveolar proteinosis [18]. Neutrophils rapidly infiltrate wound sites to clear pathogens and debris through phagocytosis, after which macrophages perform efferocytosis of apoptotic neutrophils, limiting excessive inflammation and promoting macrophage proliferation [19–21]. While neutrophils dominate the inflammatory phase, macrophages contribute to tissue repair across inflammation, proliferation, and remodeling phases [22]. Mechanistically, macrophages not only perform phagocytosis and efferocytosis but also secrete growth factors and enzymes, regulate epithelial cells, endothelial cells, fibroblasts, and myofibroblasts, and remove excess extracellular matrix, thereby modulating scar formation and pigmentation [22, 23]. Collectively, neutrophils and macrophages are essential mediators of high-quality wound healing.
Clinical evidence supports the effectiveness of GM-CSF in various wound types. Huang et al. [24] demonstrated in a randomized trial that rhGM-CSF improved granulation tissue formation, healing rates, and pain scores in chronic ulcers (pressure, venous, and diabetic foot) compared with vaseline gauze. In frostbite, rhGM-CSF decreased local inflammation, reduced bacterial load, and promoted closure [25]. Systematic reviews and meta-analyses show that rhGM-CSF accelerates healing in burn wounds for both adults and pediatric patients without systemic adverse effects [6, 7]. Additionally, rhGM-CSF has been effective in chronic venous leg ulcers [26] and is useful in reducing scar hypertrophy and pigmentation [10]. In our study, rhGM-CSF gel shortened scab detachment time, decreased bacterial positivity, and lowered pigmentation scores compared with medical collagen sponge in infants, likely due to its modulation of neutrophils and macrophages. However, the collagen sponge alone achieved slightly faster overall wound closure.
The main component of medical collagen sponge is type I collagen, which provides elasticity and protection to the skin. Experimental studies in vitro and in vivo indicate that reduced type I collagen levels delay wound healing [27]. In diabetic foot ulcers, enhanced type I collagen correlates with faster healing [28]. Recent studies confirm that type I collagen-based sponges have good biocompatibility and promote tissue repair [29, 30]. In our study, collagen sponge alone showed slightly faster healing but inferior antibacterial performance compared with rhGM-CSF gel. VSS scores for pliability and vascularity were also lower with collagen sponge alone. Importantly, the combination of rhGM-CSF and collagen sponge produced the most favorable outcomes in terms of scab detachment, healing time, bacterial negativity, and VSS scores.
Some limitations should be acknowledged. The sample size for each group was relatively small, potentially limiting the statistical power to detect differences. Although we observed statistically significant differences in scab detachment, healing time, vascularity, and total VSS score between rhGM-CSF and collagen sponge groups, the absolute differences were modest. Furthermore, this study was conducted at a single center, which may reduce generalizability. Larger, multicenter trials are needed to validate the clinical efficacy of rhGM-CSF gel and collagen sponge in pediatric burn patients.
Conclusion
Our study demonstrates that rhGM-CSF gel and medical collagen sponge each provide distinct clinical benefits due to their respective mechanisms. Combined therapy with rhGM-CSF gel and collagen sponge significantly enhances early wound healing, reduces infection risk, improves scar quality, and may optimize long-term outcomes in pediatric burn patients.
Acknowledgments: Authors are grateful to all of patients and guardians for their contribution to this research.
Conflict of interest: None
Financial support: The study was support by Science and Technology Program of Zhejiang Province (Y20220370).
Ethics statement: None