A multitude of studies have examined the link between sleep bruxism (SB) and psychological distress, producing heterogeneous outcomes. Distinct diagnostic criteria have been applied to identify SB. The purpose of this investigation was to compare the relationship between psychological distress and SB as classified by different validated approaches. Data from 45 participants were analyzed, including group-based comparisons and correlational analyses. The following diagnostic modalities for detecting SB were employed within a single cohort: self-report, clinical evaluation, polysomnography complemented by audio–video recording, and an innovative diagnostic foil with dedicated analysis software. Psychological distress was quantified using the Global Severity Index (GSI) from the Symptom Checklist-90-Standard (SCL-90-S). Scores on the GSI did not significantly distinguish subjects with and without SB, independent of the diagnostic framework applied (P > 0.05). More detailed correlational analyses of self-report and clinical findings indicated a weak-to-moderate association with the GSI (r = 0.12–0.44). Owing to the non-normal distribution of the data, formal statistical significance testing was not feasible. Indicators derived from instrumental techniques, exemplified by the SB index (SB activity events per hour) from polysomnography (PSG), displayed virtually no relationship with psychological distress (r = −0.06–0.05). Acknowledging the study’s constraints, the data imply that variation in the selected diagnostic protocol might account for discrepancies in the observed correlation between SB and psychological distress.
Introduction
Sleep bruxism constitutes a masticatory muscle activity occurring during sleep, described as either rhythmic (phasic) or non-rhythmic (tonic), and is not categorized as a movement or sleep disorder in otherwise healthy persons [1]. SB activity intensity can be understood as a spectrum, with a highly frequent, unmanaged form that may provoke clinical disorders. Among adults, SB prevalence ranges from 5.5% to 15.0% depending on the diagnostic technique used [2-4].
The origins of SB are multifactorial [1]. On a biological level, specific neurotransmitters, such as serotonin, or distinct genetic profiles have been proposed [5, 6]. Pathologies such as Parkinson’s disease and obstructive sleep apnea syndrome coincide with elevated SB rates [7, 8]. External factors like tobacco consumption show a positive link to SB [9]. A considerable body of research presents inconsistent evidence regarding a connection between SB and psychosocial dimensions like stress, maladaptive coping with stress, negative affect, or psychiatric conditions [10-14]. The nature of SB’s involvement in the emergence of painful temporomandibular disorders (TMDs) remains a topic of ongoing discussion [15-17].
In accordance with the diagnostic mode employed, SB receives a classification of possible, probable, or definite [1]: possible SB rests on a positive self-report alone, probable SB relies on a positive clinical inspection, with or without a concurrent positive self-report, and definite SB is confirmed through a positive instrumental assessment, with or without an accompanying positive self-report and/or positive clinical inspection. Non-instrumental approaches capture possible and probable SB, comprising self-report protocols and clinical appraisals. In research, questionnaires are the predominant tool for SB assessment [18]. Clinical evaluation includes a medical history obtained by interview, along with a methodical inspection of the dentition, soft and hard tissues, and the muscles of mastication [19]. Instrumental strategies span extraoral and intraoral appliances that gauge real-time SB activity. Extraoral tools feature portable electromyography (EMG) recordings that detect ongoing masticatory muscle activity with notable sensitivity and specificity (e.g., Bruxoff: sensitivity ranging from 92.3% to 100%, specificity from 76% to 91.6% when compared against the gold-standard diagnosis) [20-22]. A more sophisticated measurement modality is PSG, which captures sleep architecture alongside masticatory muscle function. This technique stands as the benchmark for SB identification, despite its labor-intensive and expensive nature [23, 24]. While audio–video monitoring to assess SB activity is optional, diagnostic precision is enhanced when it is included [25]. SB events can be operationalized and aggregated as episodes (SB-specific EMG bursts per hour; SB index) [24]. Intraoral devices, such as thin occlusal foils, record attrition patterns reflecting SB activity. A recent investigation validated an innovative diagnostic foil integrated with fully automated evaluation software, computing SB activity levels with 100% sensitivity, 80% specificity, and an area under the curve of 0.88 [26].
Consequently, SB can be defined through multiple pathways. Empirical evidence suggests that the documented interplay between SB and psychological distress shifts according to the form of SB classification. Possible SB demonstrates a positive association with both perceived and biochemically verified stress (salivary cortisol) [27, 28]. Probable SB shows positive links with manic, depressive, and anxious symptomatology, alongside negative or diminished positive coping repertoires [29-33]. Biochemically determined stress (salivary cortisol) likewise correlates positively with probable SB [29, 32]. Turning to definite SB, no meaningful relationship emerges between SB episode frequency and anxiety (assessed via the state-trait anxiety inventory) or the manifestation of stress coping styles [34].
Additionally, no significant difference separates individuals with and without definite SB regarding chronic stress [35]. Depressive features, gauged by the Beck Depression Inventory, fail to correlate significantly with the presence of definite SB or the count of SB episodes [10]. Conversely, Azevedo et al. [36] report that individuals diagnosed with definite SB exhibit markedly elevated anxiety levels. The current study explored global psychological distress, as measured by a self-report inventory.
In brief, the precise degree to which SB aligns with psychological distress remains unresolved. A contributing factor to these inconsistencies might be the selection of the diagnostic modality. As such, the central objective of the present work was to more comprehensively scrutinize SB’s association with psychological distress by deploying three standard diagnostic classifications, along with an additional novel diagnostic tool to gauge SB within the same study population. The following inquiries guided this research: (1) Do the procedures yield concordant distributions for SB and non-SB classifications? (2) Can a relationship be identified between parameters from instrumental techniques (PSG, diagnostic foil) and psychological distress? (3) Can a relationship be identified between parameters from non-instrumental techniques (self-report, clinical inspection) and psychological distress? The null hypotheses postulate the absence of agreement across diagnostic methods and the absence of a correlational tie between psychological distress and SB, as established through any of the aforementioned procedures.
Materials and Methods
The dataset examined in this case–control study comprised secondary outcome variables originating from a prior single-center validation trial [26]. The research took place between May 2019 and July 2020. Four separate diagnostic modalities or classification schemes for SB were compared: (1) self-report, (2) clinical evaluation following the International Classification of Sleep Disorders (third edition, revised text; ICSD-3 TR) criteria, (3) PSG, and (4) a diagnostic foil utilized together with automated analysis software. The diagnostic modalities are characterized further. Psychological distress was captured via a self-administered instrument. Calculation of the required sample size was based on the original study project [26]. Because the project’s purpose was to validate a novel technique, sample size considerations were established beforehand. The power calculation, calibrated to the specific research question, yielded a sample size of n = 42. With a projected attrition rate of 20%, a recruitment goal of n = 50 participants was set.
Subjects
Candidate volunteers were enrolled through notices posted at University Hospital Düsseldorf, Heinrich-Heine University, and the University of Applied Sciences Düsseldorf, as well as the institute’s internet portal and social networking channels. In keeping with the tenets of good clinical practice, any students included could hold no dependent relationship with the principal investigators. For this reason, dental students were deemed ineligible. Participation was permitted for healthy adults aged 20 to 50. General exclusion criteria ruling out a sound health status were as follows: serious psychiatric illness, substance misuse or medication/drug dependency, neurological conditions of the central and/or peripheral nervous system, and additional major physical or systemic diseases such as cardiovascular disorders, autoimmune conditions, respiratory compromise, or active inflammatory processes or malignancies, as screened via a medical history form. Women who were pregnant or nursing were likewise excluded. Supplementary dental exclusion criteria were as follows: loss of more than two molars (excluding third molars), existence of a removable dental prosthesis or extensive fixed prosthodontics, bonded orthodontic hardware, presence of marked malocclusion (i.e., anterior open bite), and existence of TMDs warranting intervention. Furthermore, no functional dental therapy could have been received within the prior six months. This includes, for instance, habitual use of an occlusal splint or receipt of physical therapy to manage TMDs.
Oral and general eligibility criteria were confirmed by a single calibrated dentist through a clinical history interview and meticulous dental inspection, as reported elsewhere [26]. The latter encompassed verification of TMD signs and symptoms in accordance with the German version of the Research Diagnostic Criteria for TMDs [37]. The presence of TMD symptoms (at a level not requiring active treatment) was treated as a covariate rather than a disqualifying factor, given that the study focused on SB. At this dental visit, maxillary and mandibular impressions were recorded for documentation and to produce a diagnostic foil. The presence of heightened psychological distress, a state that elevates risk for a mental disorder, was estimated using the SCL-90-S [38]. Individuals scoring notably high (GSI: T score ≥ 63 or 2 scales: T score ≥ 63, respectively) were withdrawn from study enrollment.
Sleep bruxism assessment
The assessments were carried out separately on four independent measurement dates. Participants were asked to complete the various measurements within a window of no more than 28 days. First, to establish possible SB, subjects answered the item “Do you grind your teeth during sleep?” embedded in a general self-assessment clinical history protocol (screening questionnaire). Second, to evaluate probable SB, the ICSD-3 TR criteria were applied via clinical interview and physical inspection [39]: (A) evidence of recurrent jaw muscle activity involving tooth grinding or clenching during sleep, plus (B) evidence of at least one of the following clinical signs or symptoms aligning with the aforementioned reports of sleep-related tooth grinding or clenching: (1) atypical tooth wear; (2) transient morning jaw muscle pain or fatigue, or temporal headache. Occlusal tooth wear reaching a minimum, the level of exposed dentin was quantified [40]. The subsequent core parameters were registered during PSG: cortical electrical activity (electroencephalography) recorded across six channels (F4-M1, C4-M1, O2-M1 with reserve leads on the opposite hemisphere), ocular motion (electrooculography), cardiac rhythm (electrocardiography), respiratory effort via piezoelectric sensors, respiratory airflow via nasal dynamic pressure sensors, limb movement (EMG), muscle tone (EMG), arterial oxygen saturation via pulse oximetry, and bodily position via motion sensors [41]. Additionally, the presence of masseter muscle hypertrophy was evaluated during voluntary clenching [42].
Third, definite SB was established from recordings obtained with a SOMNOscreen apparatus (SOMNOmedics, Randersacker, Germany) that provided simultaneous audio–video monitoring. Data collection spanned two back-to-back nights within each participant’s domestic setting [39]. Two qualified research team members arranged the equipment following a standardized sequence [43]. Bilateral EMG tracings were gathered from both the masseter and the anterior temporalis muscles. A single trained specialist evaluated the nocturnal recordings using DOMINO software (version 2.9.0, SOMNOmedics, Randersacker, Germany). Sleep architecture was staged by hand in line with the American Academy of Sleep Medicine specifications [44]. A designation of definite SB required satisfaction of these research-grade diagnostic thresholds [24]: hourly SB episode frequency (SB index) surpassing 4, hourly burst count exceeding 25, and the presence of more than 1 (at minimum 1) SB episode accompanied by grating sounds. A phasic episode consists of three or more muscle contractions (bursts), each persisting between 0.25 s and 2.00 s, with clearly distinguishable pauses without activity between them. A tonic episode entails a continuous muscle contraction lasting 2.00 s or longer. A gap of quiescence lasting a minimum of 3.00 s must separate consecutive episodes for them to be regarded as distinct. When this quiescent interval is absent at the boundary between phasic and tonic episodes, the combined event is labeled a mixed episode. A contraction qualifies for scoring when its amplitude eclipses 20% of the person-specific mean maximal masticatory muscle output recorded under maximal voluntary clenching (MVC) [24]. MVC assessments were conducted on-site before the overnight measurement. Between the two successive nights, the one yielding the greater SB index was retained for further sleep-related analyses. Oromotor actions during sleep, or EMG fluctuations tied to breathing and unrelated events, were systematically removed through synchronized audio–video inspection to isolate SB-specific phenomena [25].
The fourth and concluding session deployed the diagnostic foil alongside its custom-built analysis software. The appliance, a 0.5 mm slender overlay manufactured from biocompatible Terlux 2802 HD, comprised five chromatic strata [26]. Participants wore the device across the maxillary teeth for five uninterrupted nights. Nocturnal attrition activity etched colored wear signatures onto the foil surface, which a dedicated software package then processed in an entirely automated fashion. The resulting quantitative index, termed the pixelscore, serves as a proxy for the magnitude of SB activity, with larger values signifying more vigorous overnight grinding.
Assessment of psychological distress
The German version of the SCL-90-S self-administered questionnaire was used to assess psychological distress [38]. Nine symptomatic domains were tapped: somatization, obsessive–compulsive, interpersonal sensitivity, depression, anxiety, hostility, phobic anxiety, paranoid ideation, and psychoticism. Respondents completed the inventory on paper, after which the responses were computer-assisted processed. Normalized T-scores supplied in the test manual informed the identification of individuals to be excluded. For the core analyses, the untransformed item-level values were totaled and derived according to the manual’s formula. The current investigation focused solely on the GSI, the instrument’s composite distress metric. Its potential range is 0 to 4, with higher values indicating more severe psychological distress.
Outcome variables
The outcome variables of the present study are summarized in Table 1.
|
Table 1. Summary of outcome variables in the present study, divided by diagnostic procedure. |
|||
|
Diagnostic procedure |
Method |
Outcome |
Classification |
|
Self-report |
Single-item question: “Do you grind your teeth while asleep?” used in the screening phase |
Self-reported SB (screening) (y/n) |
Possible SB |
|
Clinical examination |
Based on ICSD-3 TR criteria: visual inspection of dentition and anamnesis interview |
SB self-report (interview) (y/n); external SB report (y/n); reported tiredness or jaw stiffness (y/n); presence of masseter muscle hypertrophy (y/n); count of teeth showing abnormal wear/attrition |
Probable SB |
|
Evaluation of the masseter muscle |
— |
Probable SB |
|
|
PSG |
Polysomnographic assessment of sleep physiology, including masseter muscle activity monitoring |
SB index: frequency index of grinding-sound episodes |
Definite SB |
|
Diagnostic sheet and software |
Fully automated computer-based evaluation of wear patterns on the diagnostic sheet |
Pixelscore |
— |
|
Psychometric self-evaluation |
SCL-90-S questionnaire |
GSI (Global Severity Index) |
— |
Note: y = yes; n = no.
Data analysis
Sample characterization relied on descriptive statistics, including means (Ms) and standard deviations (SDs). Furthermore, absolute counts and corresponding percentage shares were reported for categorical variables. Between-group comparisons (e.g., Student’s t-test) were carried out based on measurement scale and distributional characteristics to probe for systematic variation attributable to background factors such as chronological age, biological sex, and level of schooling. Inter-method alignment was quantified through Fleiss’ and Cohen’s kappa coefficients. The obtained figures were appraised using widely adopted interpretive criteria [45]: a kappa dropping under 0.00 indicates poor concordance; 0.00 to 0.20, slight; 0.21 to 0.40, fair; 0.41 to 0.60, moderate; 0.61 to 0.80, substantial; and 0.81 to 1.00, near-perfect agreement. Both group comparisons and correlational approaches were employed to explore links between psychological distress and SB. The selection among Pearson, Spearman, and biserial correlation was determined by the variable properties, namely the measurement scale and the observed distribution. Guidelines from the literature guided the interpretation of correlation coefficients [46]: coefficients spanning 0.1 to 0.3 were considered weak, those from 0.3 to 0.5 were considered medium, and those exceeding 0.5 were considered strong. All test assumptions were verified before running each statistical procedure. Shapiro–Wilk testing, coupled with visual inspection of quantile–quantile plots, served to evaluate whether the assumption of normality held. The entire set of computations was executed in the R programming environment using RStudio (v. 4.2.1; RStudio Team, Boston, MA, USA). To mitigate the risk of inflated Type I error across multiple inferential tests, the false discovery rate (FDR) was used for correction [47]. A uniform alpha threshold of P = 0.05 was adopted for all statistical determinations.
Results and Discussion
The final sample comprised 45 enrolled volunteers, of whom n = 22 (48.89%) were women and n = 23 (51.11%) were men. Participants ranged in age from 21 to 46, with an average of M = 26.40 (SD = 4.44). Those currently pursuing university degrees accounted for 78% of the sample. Every individual was assigned to either the SB or non-SB group according to each of the four diagnostic schemes. Table 2 lays out how the frequencies of SB-positive and SB-negative classifications were distributed across the different methods.
|
Table 2. Distribution of SB and non-SB across diagnostic procedures (n = 45). |
||
|
Diagnostic procedure |
Non-SB n (%) |
SB n (%) |
|
Self-report |
24 (53.33%) |
21 (46.67%) |
|
Clinical examination |
25 (55.56%) |
20 (44.44%) |
|
PSG |
35 (77.78%) |
10 (22.22%) |
|
Diagnostic sheet and software |
28 (62.22%) |
17 (37.78%) |
Descriptive summaries of particular SB metrics, organized per diagnostic approach, appear in Table 3. The pair of variables capturing self-reported SB—once from the screening instrument and once from the interview conducted during the clinical workup—aligned in 39 cases, for an 87.00% agreement.
|
Table 3. Descriptive statistics of specific SB parameters as a function of diagnostic procedure. |
||||
|
SB diagnosis based on PSG |
||||
|
Specific parameter |
Non-SB SD |
Non-SB (n = 35) M |
SB SD |
SB (n = 10) M |
|
SB index |
0.96 |
2.40 |
4.56 |
8.40 |
|
Episodes with grinding sounds index |
0.37 |
0.26 |
4.77 |
3.61 |
|
SB diagnosis based on clinical examination |
||||
|
Variable |
Non-SB (n = 25) n (%) |
SB (n = 20) n (%) |
||
|
SB self-report (interview): Yes (n = 15) |
0 (0.00%) |
15 (75.00%) |
||
|
SB self-report (interview): No (n = 30) |
25 (100.00%) |
5 (25.00%) |
||
|
SB third-party report: Yes (n = 14) |
0 (0.00%) |
14 (70.00%) |
||
|
SB third-party report: No (n = 31) |
25 (100.00%) |
6 (30.00%) |
||
|
Feeling of tiredness/stiffness: Yes (n = 15) |
2 (8.00%) |
13 (65.00%) |
||
|
Feeling of tiredness/stiffness: No (n = 30) |
23 (92.00%) |
7 (35.00%) |
||
|
Masseter hypertrophy: Yes (n = 14) |
4 (16.00%) |
10 (50.00%) |
||
|
Masseter hypertrophy: No (n = 31) |
21 (84.00%) |
10 (50.0%) |
||
|
Variable |
Non-SB SD |
Non-SB M |
SB SD |
SB M |
|
Number of teeth with abnormal attrition |
5.40 |
6.00 |
6.68 |
7.90 |
|
SB Diagnosis Based on Diagnostic Sheet |
|
|
|
|
|
Group |
Non-SB SD |
Non-SB (n = 18) M |
SB SD |
SB (n = 17) M |
|
Pixelscore |
139.00 |
168.69 |
735.72 |
1274.23 |
Note: The bold headings divide the descriptive statistics by diagnostic classification and the distribution of the specific parameter values.
Agreement between diagnostic procedures
An initial inquiry tested the degree to which the four approaches produced matching SB and non-SB verdicts. Collapsing across all techniques, Fleiss’ κ reached 0.39 (z = 6.33, P < 0.01), a figure that qualifies as a moderate level of inter-method agreement [45]. A marked asymmetry was evident in the PSG-based groupings: only 10 individuals (22.22%) met the criteria for SB, whereas 35 (77.78%) did not. In contrast, self-report yielded a much more balanced picture, with 21 (46.67%) screening positive for SB and 24 (53.33%) screening negative. Identical classification outcomes across all four procedures were observed in exactly 23 participants (51.11%). The remaining subset showed inconsistent designations across diagnostic lenses; one illustrative case involved a participant flagged as SB by self-report but deemed non-SB by the other three modalities. Table 4 presents the pairwise correspondences with polysomnography as the benchmark, and Cohen’s kappa is used to gauge agreement. Both the clinical assessment and the self-report questionnaire showed only moderate concordance with PSG [45]. The diagnostic foil, meanwhile, displayed substantial agreement with the PSG reference [45].
|
Table 4. Agreement of diagnoses of all procedures with diagnosis using the gold-standard reference, PSG (n = 45). |
|||
|
Diagnostic Method |
Statistics |
Non-SB (n = 35) n (%) |
SB (n = 10) n (%) |
|
Self-report |
|
|
|
|
SB (n = 21) |
κ = 0.22 |
14 (40.00%) |
7 (70.00%) |
|
non-SB (n = 24) |
|
21 (60.00%) |
3 (30.00%) |
|
Clinical examination |
|
|
|
|
SB (n = 20) |
κ = 0.24 |
13 (37.14%) |
7 (70.00%) |
|
non-SB (n = 25) |
|
22 (62.86%) |
3 (30.00%) |
|
Diagnostic sheet and software |
|
|
|
|
SB (n = 17) |
κ = 0.64 |
7 (20.00%) |
10 (100.00%) |
|
non-SB (n = 28) |
|
28 (80.00%) |
0 (0.00%) |
Group comparison between SB diagnosis and psychological distress
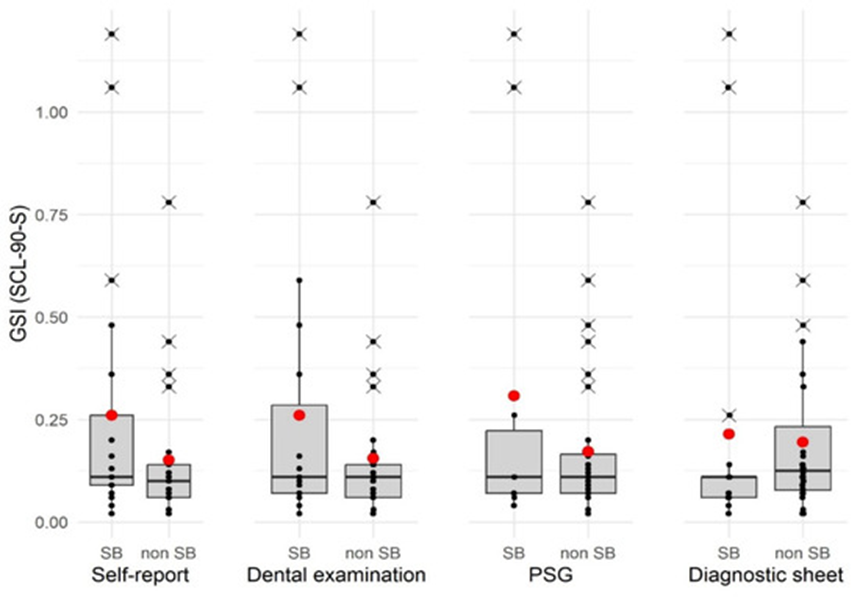
The distribution of GSI scores from the SCL-90-S across the entire sample was clearly right-tailed, with M = 0.20 and SD = 0.26 (median = 0.11, observed range = 0.02–1.19). Normality was decisively rejected (W = 0.64, P < 0.001), with the Shapiro–Wilk test corroborating the impression from the quantile–quantile plot. Figure 1 presents a boxplot depiction of GSI readings stratified by diagnostic status and classification methodology.
|
|
|
Figure 1. Boxplots of GSI (SCL-90-S) data divided by bruxism classification and diagnosis procedure. The red dots indicate the mean values. The black dots indicate individual data values. Data values marked with a cross are outliers. |
The boxplots show that estimates of central tendency are not uniform. Due to the pull exerted by outlying data points, the arithmetic means shift perceptibly upward, whereas the medians remain virtually unchanged across all groupings, regardless of the diagnostic framework. Given the skewed distribution, group contrasts were conducted using Mann–Whitney U tests, with subsequent p-value correction for multiplicity via the FDR approach. Table 5 collates the descriptive figures for the GSI, sorted by SB status (present vs. absent) within each diagnostic modality, along with the corresponding inferential test results. No contrast approached statistical significance.
|
Table 5. Descriptive statistics and comparison of group differences of GSI as a function of SB diagnosis by respective procedure. |
||||||
|
The SB diagnosis method |
Group |
P† |
Statistics |
Median |
SD |
M |
|
Self-report |
Yes (n = 21) |
0.400 |
W = 190.50 |
0.11 |
0.32 |
0.26 |
|
No (n = 24) |
|
|
0.10 |
0.17 |
0.15 |
|
|
Clinical examination |
Yes (n = 20) |
0.572 |
W = 215.00 |
0.11 |
0.33 |
0.26 |
|
No (n = 25) |
|
|
0.11 |
0.17 |
0.16 |
|
|
PSG |
Yes (n = 10) |
0.945 |
W = 172.00 |
0.11 |
0.44 |
0.31 |
|
No (n = 35) |
|
|
0.11 |
0.17 |
0.17 |
|
|
Diagnostic sheet and software |
Yes (n = 17) |
0.400 |
W = 293.00 |
0.11 |
0.35 |
0.21 |
|
No (n = 28) |
|
|
0.12 |
0.19 |
0.20 |
|
Note: † significance value controlled with FDR.
Correlational analyses of specific SB parameters and psychological distress
The analytical plan next proceeded to a set of correlation calculations designed to estimate, firstly, the empirical link between a binary SB classification (derived from each respective method) and the GSI and, secondly, the link between more fine-grained diagnostic indicators—some continuously scaled, some dichotomous—and the GSI. The full array of coefficients is displayed in Table 6.
|
Table 6. Correlation analyses of specific SB parameters and SCL-90-S GSI. |
||||
|
Assessment domain |
Parameter |
P† |
rs |
rb |
|
Self-report |
SB self-report (screening) / SB diagnosis |
– |
– |
0.27 |
|
Clinical examination |
SB diagnosis |
– |
– |
0.26 |
|
SB self-report (interview) |
– |
– |
0.44 |
|
|
SB third-party report |
– |
– |
0.20 |
|
|
Feeling of tiredness/stiffness |
– |
– |
0.24 |
|
|
Masseter hypertrophy |
– |
– |
0.12 |
|
|
Number of teeth with attrition |
0.580 |
0.22 |
– |
|
|
PSG |
SB diagnosis |
– |
– |
0.31 |
|
SB index |
0.715 |
0.05 |
– |
|
|
Episodes with grinding sounds index |
0.715 |
−0.06 |
– |
|
|
Diagnostic sheet |
SB diagnosis |
– |
– |
0.05 |
|
Pixelscore |
0.715 |
−0.11 |
– |
|
Note: rb = biserial correlation coefficient, rs = Spearman correlation coefficient, † significance value controlled with FDR.
Whether a Spearman coefficient (rs) or a biserial coefficient (rb) was selected depended on the measurement properties of the variable in question. Significance evaluation was possible for the Spearman estimates. Given that the GSI departed markedly from a Gaussian shape, the z-based significance test ordinarily applied to biserial correlations could not be legitimately performed [48]; P-values for these coefficients are thus deliberately omitted. None of the Spearman-derived estimates reached significance. The overall pattern of effect sizes was predominantly weak. A single departure from this trend was observed: the biserial correlation between SB self-acknowledged during the clinical interview and the GSI was rb = 0.44. This pattern suggests that individuals who affirm tooth grinding when directly questioned in the clinical setting tend to report higher levels of global psychological distress. Other dental parameters failed to show comparable associations, as evidenced by the negligible relationship between masseter hypertrophy and the GSI (rb = 0.12). The hourly rate of masticatory muscle contractions, expressed as the SB index, proved essentially unrelated to the GSI (rs = 0.05), while the pixelscore derived from the diagnostic foil bore a faint inverse relationship with the distress measure (rb = −0.11).
Based on the statistical between-group tests, the level of psychological distress, as captured by the GSI of the SCL-90-S, did not meaningfully separate participants with possible, probable, or definite SB from those without any of these subtypes. A more granular exploration uncovered a moderate positive, albeit non-significant, link between self-endorsed SB recorded within the clinical interview context and psychological distress. In stark contrast, PSG-extracted variables, such as the hourly SB index, demonstrated essentially null associations with distress scores. Put differently, neither the rate of masticatory muscle contractions nor the occurrence of grinding noises bore any appreciable connection to psychological distress. A weakly negative and likewise non-significant relationship emerged between contemporaneous SB activity—quantified via an innovative diagnostic platform featuring fully automated analysis—and psychological distress. The mutual correspondence across the four diagnostic schemes proved merely moderate overall. Head-to-head comparisons revealed that agreement between self-reported and clinician-ascertained SB, as well as between self-reported SB and definite SB, was limited. The novel intraoral device (diagnostic foil), however, showed substantial alignment with PSG. This pattern of modest concordance, especially between clinically detected SB and instrumental benchmarks, is consistent with findings from other research groups [49, 50].
The outcomes touching on psychological distress and SB are difficult to reconcile with investigations that have documented substantial divergences in SCL-90-R overall scores and anxiety subscale values between cohorts with and without possible and probable SB [51, 52]. One must bear in mind that Ahlberg et al. [52] worked with a markedly larger sample (n = 750) of exclusively irregular shift workers, whereas Bayar et al. [51] restricted recruitment to patients visiting a military hospital. The present sample was heavily skewed toward university students, a characteristic that might hamper efforts to draw parallels with those earlier reports. To the authors’ knowledge, no subsequent study has specifically contrasted probable SB with non-SB using the SCL-90-R. Even so, other investigators have succeeded in showing that probable bruxers exhibit heightened stress and diminished mental health, as gauged through both subjective self-reports and objective markers [13, 29-33]. Set against this body of evidence, the null finding observed here for the probable versus non-probable SB comparison appears somewhat unexpected.
Relatively sparse research has directly tackled the intersection of instrumentally recorded SB activity and SCL-90-S-measured psychological distress. Regarding objectively registered SB, the findings presented here run counter to those reported by Shen et al. [53], who found both a significant group-level distinction and significant positive correlations between SB episode frequency and SCL-90-R dimensions. The data, however, align with the broader trends articulated by Manfredini et al. [54]: their meta-analytic work established that SB indices derived without instrumentation tend to align more closely with psychosocial parameters than indices obtained through instrumental recordings. In the current dataset, on a purely descriptive level, the coefficients linking non-instrumental SB markers (e.g., self-identified SB) to psychological distress indeed exceed those linking instrumental SB metrics (e.g., the SB index) to psychological distress.
Some broad and procedural limitations merit commentary. The SCL-90-S was administered once, exclusively at the screening stage. For a sizeable portion of participants, the gap between the initial evaluation and the eventual PSG appointment ranged from 2 to 3 weeks. It is worth noting, nevertheless, that the SCL-90-S exhibits generally solid test–retest reliability, suggesting that the initial distress values remain reasonably constant over such intervals [38]. It seems plausible that the range of psychometric variation within the sample was compressed. This can plausibly be traced to the fact that the SCL-90-S initially functioned as a gatekeeping tool designed to filter out potential participants who screened positive for a suspected psychiatric condition. The heavily lopsided representation of SB categories (e.g., definite SB, n = 10; non-SB, n = 35) alongside the modest total number of participants may further impede the nuanced interpretation of results.
A key asset of this work rests in its deployment of four complementary diagnostic frameworks—two reliant on self-report or clinical observation and two grounded in instrument-based measurement—applied to a single participant pool at separate evaluation points. The results’ configuration supports the hypothesis that selecting a diagnostic lens may color the strength and direction of the relationship between SB and psychological distress. One could argue that SB is best conceptualized as a multidimensional entity, in which different diagnostic routes access distinct dimensions of that entity. A possible inference is that the actual muscular and grinding phenomena show a near-zero or even marginally inverse relationship with psychological distress. An alternative line of reasoning proposes that self-reported SB, whether endorsed on a paper form or expressed during a dental examination, may also serve as a barometer of the individual’s overall distress level.
In light of the limitations outlined, several directions for future research crystallize to permit a deeper dissection of the SB–psychological distress interface. Firstly, capturing both psychological distress and SB activity in a temporally dense, repeated manner would enhance the capacity to track how shifts in one domain map onto shifts in the other. Secondly, to achieve adequately powered samples, studies that capitalize on less cumbersome devices—such as portable EMG monitors or intraoral appliances, such as diagnostic foils—represent a pragmatic way forward [20, 26, 55, 56]. Regarding the diagnostic foil in particular, the current dataset shows strong concordance with the gold-standard PSG diagnosis [25]. It could also be instructive to probe which additional factors drive individuals to perceive themselves as bruxers. Self-identification of SB is inherently problematic, given that the behavior occurs during unconsciousness. Associated phenomena, such as morning jaw stiffness or fatigue, could just as readily stem from alternative causes, notably awake bruxism or TMDs. Hence, for future investigative efforts, it would be valuable to disentangle the contributions of awake bruxism, SB, and TMDs to psychological stress, ideally through the systematic use of instrumental recording modalities.
Conclusion
The alignment between specific instrumental and non-instrumental approaches in categorizing individuals as SB-positive or SB-negative is limited. It can be deduced that each procedure captures partially distinct facets of the SB construct. The strength of association between psychological distress and instrumentally determined SB (via PSG and the diagnostic foil) is descriptively minimal. The strength of association between psychological distress and non-instrumentally determined SB (via self-report and clinical inspection) is, in descriptive terms, somewhat stronger and positively oriented. Synthesizing the evidence while weighing the study’s constraints, the following can be offered as guidance for clinical settings and future investigation. When SB is assessed non-instrumentally, its association with psychological distress is more robust than when it is assessed instrumentally. That said, should psychological distress be communicated or detected alongside possible or probable SB, clinicians would do well to accord it proper attention, and a referral for psychotherapeutic support may be advised.
Acknowledgments: None
Conflict of interest: None
Financial support: This research was funded by grants from the North Rhine-Westphalia Patent Validation Program of the European Regional Development Fund (ERDF, or EFRE in German, EFRE-0400096) and by Mr. Wolfgang Hirsch.
Ethics statement: This study was conducted in accordance with the Declaration of Helsinki and approved by the Ethics Committee of Heinrich Heine University, Düsseldorf (registration number 2017094440, date of approval: 29 March 2018). The newly developed diagnostic procedure was registered with the government as a proof-of-medical-product trial (EUDAMED No. CIV-17-09-021645; ClinicalTrials.gov ID: NC T03325920).
Informed consent was obtained from all subjects involved in the study.