The underlying cellular and molecular mechanisms that trigger atrial fibrillation (AF) remain poorly understood. Previous studies have identified increased Rho kinase (ROCK) expression and elevated phosphorylation of myosin-phosphatase-target subunit-1 (MYPT-1), a marker of ROCK activity, in AF patients. These changes are linked to higher levels of connexin 40 (Cx40), a gap junction protein critical for fast electrical signal propagation in the heart. AF is particularly common in dialysis patients, who also show increased MYPT-1 phosphorylation correlating with left ventricular (LV) hypertrophy. Considering ROCK’s known role in cardiovascular and renal remodeling, which may compromise intercellular electrical coupling and promote AF onset, we assessed MYPT-1 phosphorylation, Cx40 expression, and their interrelationship in dialysis patients with AF. Mononuclear cells from dialysis patients with AF (DPAFs), dialysis patients with normal sinus rhythm (DPs), and healthy controls (C) were analyzed using western blotting, and M-mode echocardiography measured LV mass and left atrial systolic volume. Phospho-MYPT-1 was markedly elevated in DPAFs compared to DPs and controls (1.57 ± 0.17 vs. 0.69 ± 0.04 vs. 0.51 ± 0.05, p < 0.0001), while DPs also showed higher levels than controls (p = 0.009). Similarly, Cx40 expression was highest in DPAFs (1.23 ± 0.12) relative to DPs (0.74 ± 0.03) and controls (0.69 ± 0.03, p < 0.0001). In DPAFs, phospho-MYPT-1 positively correlated with Cx40 expression (p < 0.001), left atrial volume (p = 0.013), and LV mass (p = 0.014). Treatment with the ROCK inhibitor fasudil reduced both MYPT-1 phosphorylation (p < 0.01) and Cx40 levels (p = 0.03). These results implicate ROCK signaling and Cx40 in the pathogenesis of AF in dialysis patients, suggesting that targeting the ROCK pathway could provide novel mechanistic insights and potential therapeutic avenues.
Introduction
Atrial fibrillation (AF) represents one of the most prevalent sustained cardiac arrhythmias [1], with its development strongly influenced by structural and electrical remodeling of atrial myocytes, as well as broader cardiac remodeling [2]. The renin–angiotensin–aldosterone system (RAAS) has been recognized as a critical signaling network driving the molecular events that promote atrial fibrosis and AF [3]. Evidence for RAAS’s central role comes not only from clinical trials demonstrating that RAAS blockade can prevent both initial and recurrent AF but also from epidemiological observations linking AF with hypertension and kidney disease [4]. Given the complexity of RAAS, which involves numerous interconnected cellular signaling pathways, dissecting the specific mechanisms by which RAAS contributes to atrial fibrosis and electrical disturbances is important both for clinical understanding and for guiding the development of novel pharmacological strategies.
Angiotensin II (Ang II), the principal effector of RAAS, exerts its effects primarily via the type 1 Ang II receptor (AT1R). One major downstream consequence of AT1R activation is the generation of reactive oxygen species (ROS), which in turn stimulate mitogen-activated protein kinase (MAPK) pathways directly involved in fibrosis and remodeling. Both AT1R and TGFβ1 are known to activate NADPH oxidase, further amplifying ROS production [3]. Another signaling cascade triggered by AT1R involves protein kinase C (PKC), leading to upregulation of nuclear factor-kB and activator protein via phospholipase C-mediated increases in phosphatidylinositol signaling [1]. More recently, activation of the Janus kinase (JAK) pathway and its downstream effectors has also been linked to AT1R signaling, contributing to atrial fibrosis and remodeling in failing hearts [5].
Connexins (Cxs), the main components of cardiac gap junctions, are essential for rapid electrical conduction between cardiomyocytes [6,7]. While alterations in Cx expression are well-established features of atrial structural remodeling, their regulation by Ang II remains less clearly defined. In a chronic kidney disease animal model, Qiu et al. [8] demonstrated that increased susceptibility to AF was associated with cardiac remodeling, including decreased Cx40 expression alongside elevated Cx43 and N-cadherin levels. Importantly, these connexin changes were mediated by Ang II via AT1R-dependent activation of Rho GTPase proteins [8]. This is significant given the established role of the RhoA/Rho kinase (ROCK) pathway in the development and maintenance of hypertension in both experimental models and humans [9]. Such findings raise questions about the precise contributions of the RhoA/ROCK pathway downstream of Ang II in the molecular mechanisms underlying AF. Supporting this, Chen et al. [10] recently reported that left atrial appendages from patients with documented AF exhibited increased ROCK expression, elevated phosphorylation of its downstream target MYPT-1 (a recognized marker of ROCK activity), and higher Cx40 levels.
In this study, we aimed to quantify MYPT-1 phosphorylation, as an indicator of RhoA/ROCK pathway activity, and Cx40 expression in circulating mononuclear cells from dialysis patients with either sinus rhythm or AF. We also investigated the relationship between these markers and compared their levels in dialysis patients to those in healthy controls. Additionally, the effects of the ROCK inhibitor fasudil on MYPT-1 phosphorylation and Cx40 expression were evaluated to explore potential modulatory mechanisms.
Patients and Methods
Patients
This study enrolled individuals with end-stage renal disease (ESRD) who were on chronic dialysis at the Nephrology, Dialysis, and Transplantation Unit, University of Padova. A total of 22 patients were included: 11 with permanent atrial fibrillation (DPAF; 7 males, 4 females, aged 49–81) and 11 dialysis patients without AF (DP; 7 males, 4 females, aged 53–82). All participants had been receiving low-flux bicarbonate dialysis using a polysulfone dialyzer (1.8 m²) for 210–240 minutes per session, three times weekly, for at least one year (range: 1–5 years). Dialysis was performed with ultrapure dialysate, and all patients had vascular access via an arteriovenous fistula, with an average Kt/V of 1.43 ± 0.07.
Inclusion criteria required patients to be free from major comorbidities, including chronic obstructive pulmonary disease, heart failure, or cancer, and they must not have been hospitalized in the six months prior to enrollment. ESRD etiologies were chronic glomerulonephritis (n = 3), diabetic nephropathy (n = 8), nephroangiosclerosis (n = 4), adult polycystic kidney disease (n = 1), IgA nephropathy (n = 2), reflux nephropathy (n = 1), amyloidosis (n = 1), and unknown causes (n = 2). All participants had normal CRP levels (2.30 ± 1.30 mg/L) and no clinical signs of infection or inflammation.
All dialysis patients were treated with epoetin (4000–12,000 UI/week). Among the DPAFs, six received warfarin, and five were treated with low-molecular-weight heparin. Blood pressure ranged from 135/86 to 155/92 mmHg, with patients receiving antihypertensive therapy such as calcium channel blockers (amlodipine or lercanidipine, 10–20 mg/day), ACE inhibitors (ramipril 5 mg/day), angiotensin receptor blockers (olmesartan 20 mg/day), α-blockers (doxazosin 2–4 mg/day), or combinations. None were on lipid-lowering agents.
Vitamin D supplementation (1.25 dihydroxyvitamin D3, 25 µg every two days) and calcium were administered in 10 patients. Phosphate binders included sevelamer HCl (3200–4000 mg/day, n = 2), calcium carbonate (2500–3000 mg/day, n = 7), and lanthanum carbonate (2250 mg/day, n = 3). Additionally, all patients received folic acid (10 mg) post-dialysis.
A control group of healthy volunteers (n = 11; 7 males, 4 females, aged 37–65) was recruited from staff members at the same unit. The study adhered to the Declaration of Helsinki, and informed consent was obtained from all participants.
Methods
Isolation of mononuclear cells
Blood samples were processed on the day of collection. Peripheral blood mononuclear cells (PBMCs) were isolated from 35 mL of EDTA-treated blood. After removing plasma, PBMCs were separated using a density gradient centrifugation protocol with Lympholyte-H (Cedarlane, Burlington, ON, Canada).
Western blot analysis of MYPT-1 phosphorylation and Cx40 expression
The expression levels of MYPT-1, its phosphorylation status, and Cx40 were determined via western blotting following established protocols [9]. Briefly, total protein from PBMCs of both patients and controls was extracted using a lysis buffer containing Tris-HCl (20 mmol/L), NaCl (150 mmol/L), EDTA (5 mmol/L), Niaproof (1.5 percent), NaVO4 (1 mmol/L), SDS (0.1%), and PMSF (0.5 mmol/L), supplemented with protease and phosphatase inhibitor cocktails (Roche and Sigma-Aldrich). Samples were kept on ice and sonicated three times using a UP200S sonicator (Hielscher GmbH, Germany). Supernatants were collected and stored at −80 °C for subsequent analysis. Protein concentrations were measured using a bicinchoninic acid assay (BCA Protein Assay, Pierce). Proteins were separated by SDS-PAGE (Tris pH 8.3) and transferred onto nitrocellulose membranes using a Hoefer TE 22 Mini Tank Transfer system with a buffer containing glycine (39 mmol/L), Tris base (48 mmol/L), SDS (0.037%), and 20% methanol. Membranes were blocked with 5% non-fat milk in Tween-PBS and incubated overnight with primary antibodies against phospho-MYPT-1 (Thr853), total MYPT-1 (Cell Signaling), or Cx40 (Abcam). β-actin (Sigma-Aldrich) served as a loading control. HRP-conjugated secondary antibodies (Amersham Pharmacia) were used, and signals were detected by chemiluminescence with SuperSignal West Pico substrate (Pierce) using an Amersham Imager 600. Protein bands were quantified by densitometry using NIH ImageJ software (16-bit grayscale TIFF). Target protein levels were normalized to β-actin, and the ratio of phospho-MYPT-1/β-actin to MYPT-1/β-actin was calculated to estimate ROCK activity.
ROCK inhibition with fasudil
To explore the effect of ROCK inhibition on Cx40 expression, PBMCs from five representative DPAFs were treated with the ROCK inhibitor fasudil (Sigma-Aldrich). For each patient, three aliquots containing 5 × 10⁶ PBMCs were incubated in RPMI-1640 medium with 0, 500, or 1000 µM fasudil for 3 hours at 37 °C. Following incubation, cells were washed three times with PBS, and total protein was extracted and analyzed as described above to quantify changes in MYPT-1 phosphorylation and Cx40 expression.
Echocardiography
Left ventricular (LV) mass and geometry were assessed using M-mode echocardiography following Devereux et al. [11]. LV mass was indexed to body surface area, with normal reference values defined as <116 g/m² for males and <96 g/m² for females [12]. Relative wall thickness (RWT) was calculated according to established guidelines; LV hypertrophy (LVH) was classified as concentric if RWT ≥0.42 and eccentric if <0.42 [13]. Left atrial systolic volume was also measured.
Statistical analysis
Continuous variables were first tested for normality using the Kolmogorov–Smirnov test. Data with normal distribution are presented as mean ± standard deviation, whereas non-normally distributed data are expressed as median (interquartile range). Standard error of the mean (SEM) was used for error bars. Categorical data are reported as counts and percentages. Group comparisons were performed using ANOVA, with a p-value <0.05 considered statistically significant. Associations between variables were evaluated using the Pearson correlation coefficient (r). Statistical analyses were conducted using SPSS Version 22 (IBM, New York, NY, USA).
Results
MYPT-1 phosphorylation status
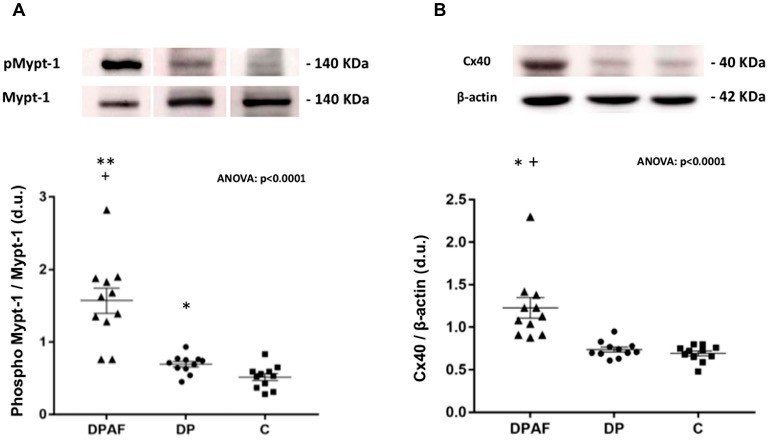
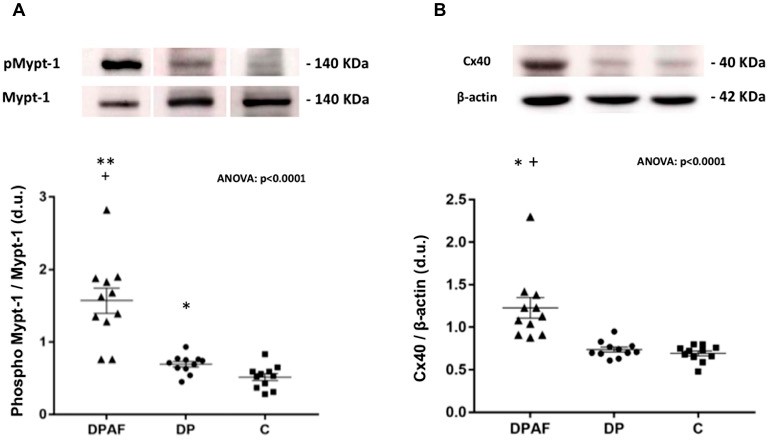
In individuals with end-stage renal failure receiving dialysis, the proportion of phosphorylated MYPT-1 relative to total MYPT-1 in PBMCs was markedly elevated in those with atrial fibrillation (DPAFs) compared to both dialysis patients without AF (DPs) and healthy controls (C), with values of 1.57 ± 0.17, 0.69 ± 0.04, and 0.51 ± 0.05, respectively (ANOVA: p < 0.0001).
Notably, DPAFs exhibited significantly higher phospho-MYPT-1 levels than both DP and control groups (p < 0.0001 for each comparison). Moreover, DP patients also showed a significant increase in phospho-MYPT-1 when compared with healthy controls (p = 0.009) (Figure 1A).
|
|
|
Figure 1. (A) Quantitative densitometry of the phospho-MYPT-1 (myosin-phosphatase-target subunit-1) relative to total MYPT-1 in mononuclear cells from dialyzed patients with atrial fibrillation (DPAFs, n = 11), dialyzed patients without atrial fibrillation (DPs, n = 11), and healthy controls (C, n = 11). The upper panel displays representative western blot bands for phosphorylated MYPT-1 and total MYPT-1 from a single subject in each group (DPAF, DP, C). Statistical significance: ** p < 0.0001 versus DP; + p < 0.0001 versus C; * p = 0.009 versus C.(B) Densitometric evaluation of connexin 40 (Cx40) normalized to β-actin in mononuclear cells of DPAFs (n = 11), DPs (n = 11), and healthy controls (C, n = 11). Representative western blot images of Cx40 and β-actin from one individual per group are shown in the upper panel. Statistical significance: * p < 0.001 versus DP; + p < 0.001 versus C |
Cx40 protein expression
Cx40 levels in mononuclear cells were markedly elevated in DPAFs compared to DPs and healthy controls (1.23 ± 0.12 vs. 0.74 ± 0.03 vs. 0.69 ± 0.03, ANOVA: p < 0.0001; Figure 1B). Specifically, DPAFs exhibited significantly higher Cx40 expression than both DPs and controls (p < 0.001 versus each group). While DPs showed a trend toward increased Cx40 relative to controls, this difference did not achieve statistical significance.
Correlation analyses in DPAFs
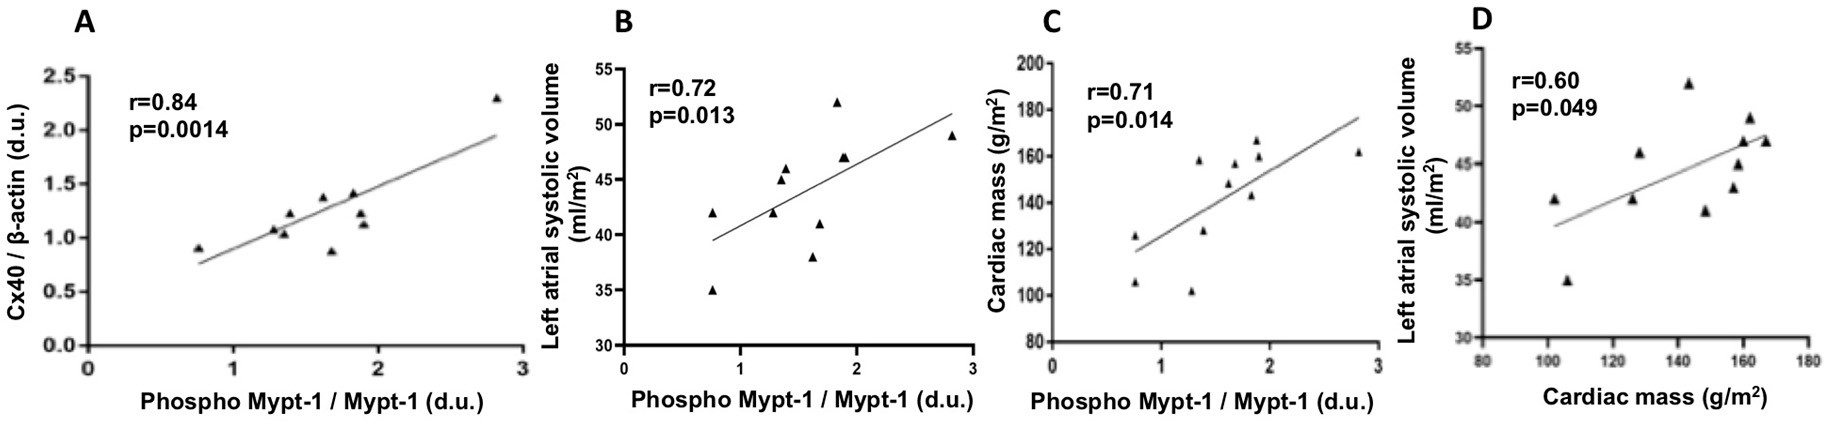
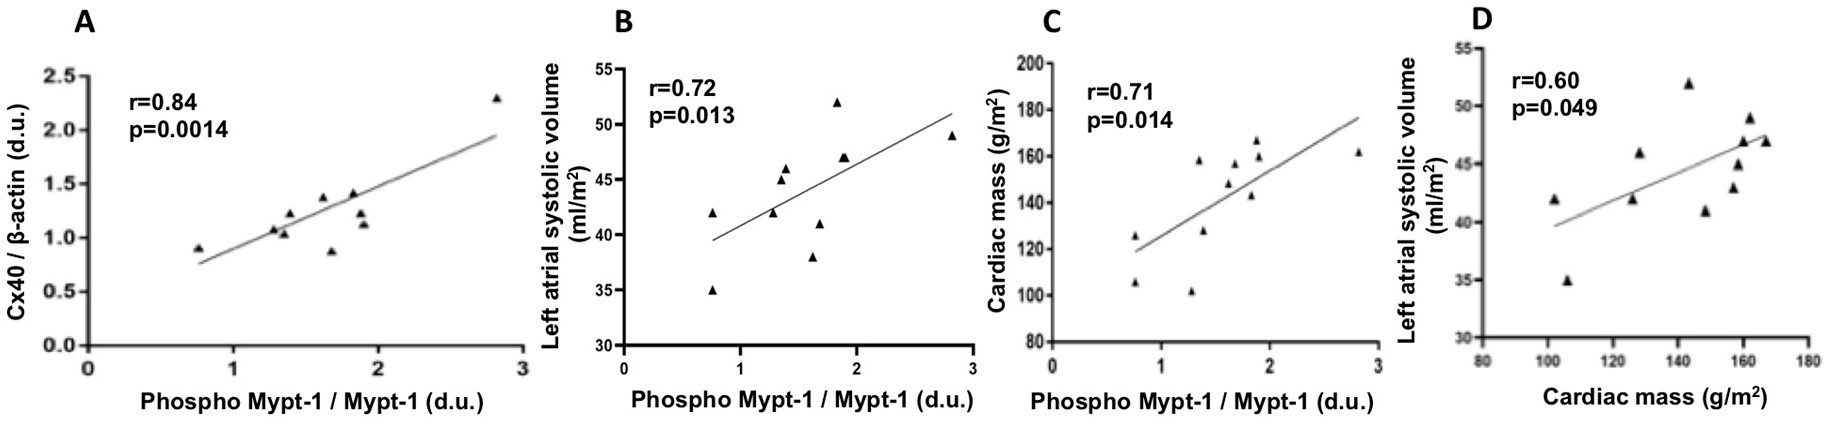
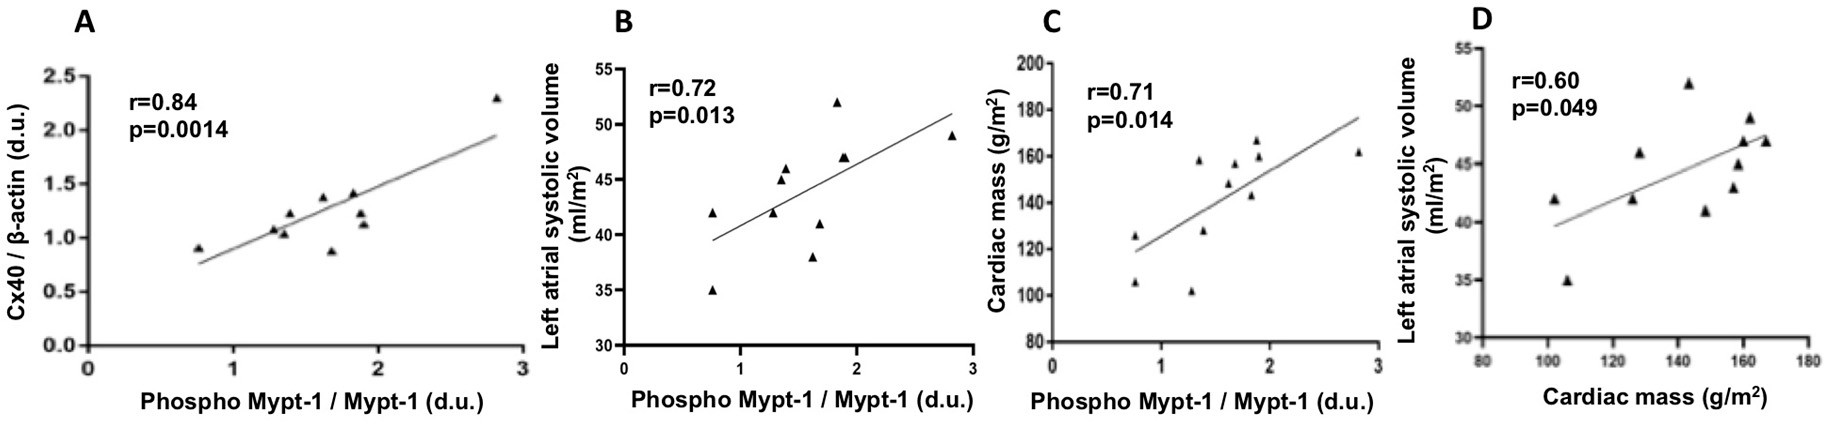
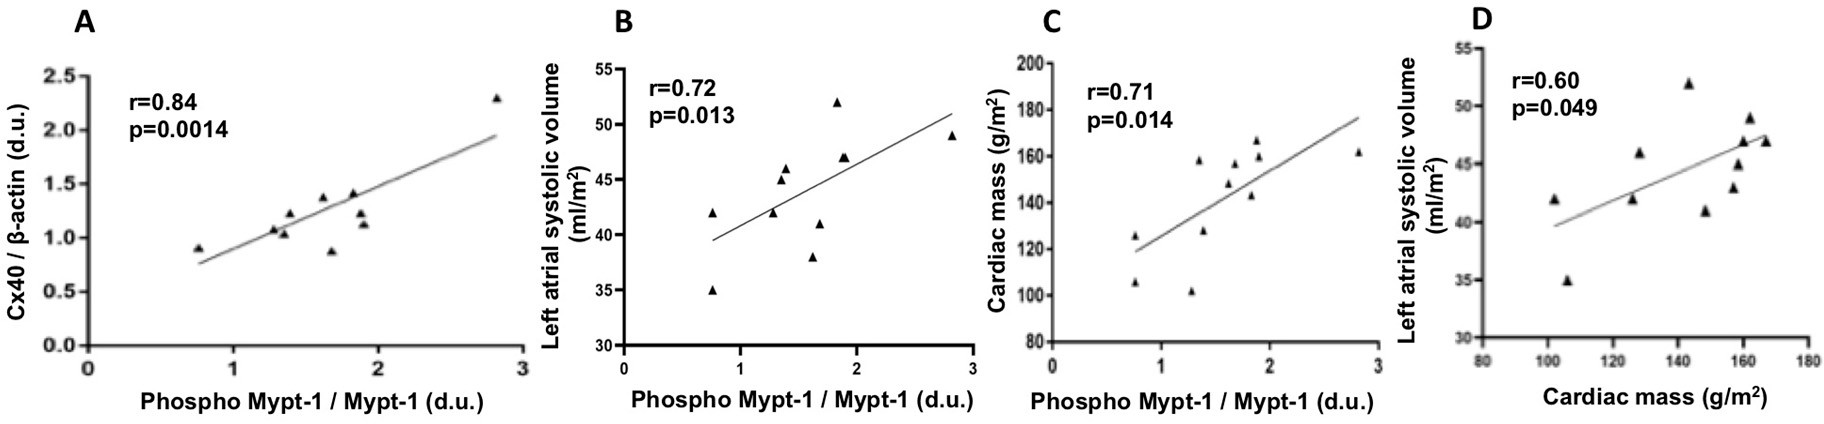
In DPAFs, MYPT-1 phosphorylation demonstrated a strong positive correlation with Cx40 protein levels (r = 0.84, p = 0.0014). Additionally, MYPT-1 phosphorylation was significantly associated with left atrial systolic volume (r = 0.72, p = 0.013) and cardiac mass (r = 0.71, p = 0.014). A significant correlation was also observed between cardiac mass and left atrial systolic volume in this group (r = 0.60, p = 0.049; Figure 2).
|
|
|
Figure 2. (A) Relationship between phospho-MYPT-1 levels and Cx40 in DPAFs. (B) Association of phospho-MYPT-1 with left atrial systolic volume. (C) Link between phospho-MYPT-1 and cardiac mass. (D) Correlation between cardiac mass and left atrial systolic volume in DPAFs |
ROCK inhibition with fasudil: Effects on MYPT-1 phosphorylation and Cx40
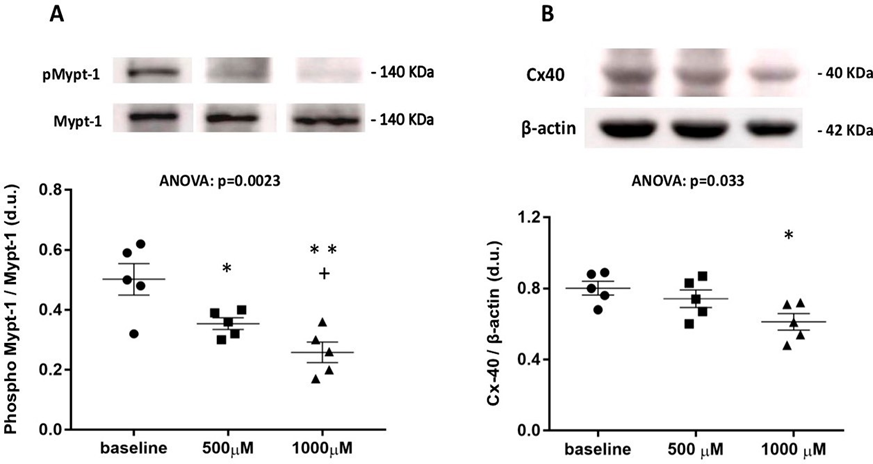
PBMCs from five representative DPAFs were treated with Fasudil at concentrations of 500 µM and 1000 µM. Both doses led to a significant reduction in MYPT-1 phosphorylation (ANOVA: p = 0.0023). Phosphorylated MYPT-1 decreased from 0.50 ± 0.05 at baseline to 0.34 ± 0.02 after 500 µM (p = 0.03) and further to 0.26 ± 0.03 after 1000 µM (p = 0.005). Moreover, the reduction between the two Fasudil concentrations was statistically significant (p = 0.04; Figure 3).
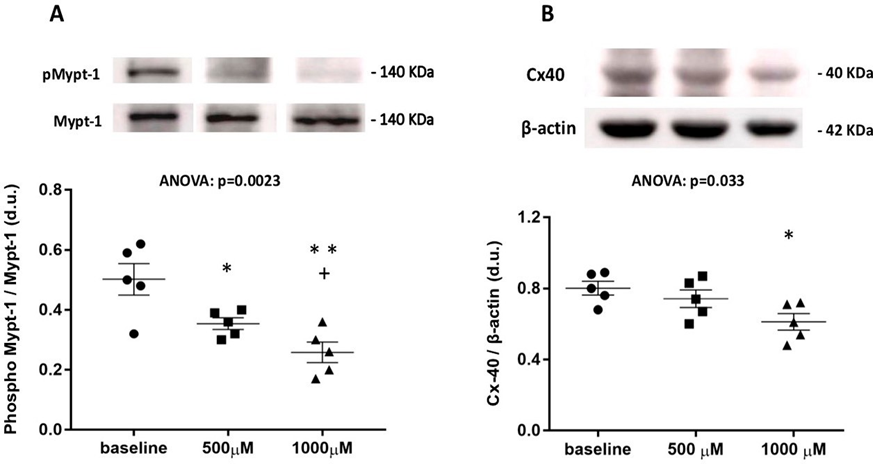
Treatment with Fasudil also lowered Cx40 levels in the same PBMCs (ANOVA: p = 0.033). The decrease reached statistical significance only at 1000 µM: baseline 0.80 ± 0.04, 500 µM 0.74 ± 0.05 (not significant), and 1000 µM 0.61 ± 0.05 (p = 0.014). Comparisons between baseline and 500 µM, as well as between 500 µM and 1000 µM, did not show significant differences (Figure 3).
|
|
|
Figure 3. (A) Quantitative densitometry of phospho-MYPT-1 in PBMCs from five DPAFs following treatment with Fasudil at 500 µM and 1000 µM. Representative western blot images of phosphorylated MYPT-1 from one patient are shown at the top. Statistical annotations: ** p = 0.005 versus baseline; + p = 0.04 versus 500 µM; * p = 0.03 versus baseline. (B) Densitometric evaluation of Cx40 in PBMCs from the same DPAFs after Fasudil exposure. Representative Cx40 western blot from one patient is displayed. * p = 0.014 versus baseline |
Relationship between cardiac remodeling and MYPT-1 phosphorylation
Left ventricular mass was elevated in DPAFs, measuring 148.6 ± 5.3 g/m² in males and 123.4 ± 19.4 g/m² in females, compared with reference ranges (<116 g/m² for males, <96 g/m² for females [12]). In these patients, left ventricular mass showed a significant positive correlation with MYPT-1 phosphorylation (r = 0.71, p = 0.014; Figure 2). Left atrial systolic volume was also increased in DPAFs relative to DPs (44.45 ± 1.38 mL/m² vs. 35.09 ± 2.62 mL/m², p = 0.005) and was significantly associated with MYPT-1 phosphorylation. Furthermore, a significant relationship was observed between cardiac mass and left atrial systolic volume in DPAFs (Figure 2).
Discussion
Atrial fibrillation (AF) involves structural, electrical, and contractile remodeling of atrial myocytes. Key molecular drivers of this remodeling include interconnected pathways such as RAAS, TGFβ1 [14], extracellular signal-regulated kinases (ERK) [15], and oxidative stress signaling [16].
AF is the most common arrhythmia in patients with chronic kidney disease (CKD) and those undergoing dialysis, likely due to aberrant RAAS activation. Previous studies demonstrated that aldosterone’s pro-fibrotic and pro-inflammatory effects are mediated through ROCK activation [17], leading to cardiovascular and renal remodeling, as well as impaired intercellular conduction. These alterations promote AF onset and maintenance by reducing atrial wavelength [7,18].
Our results indicate that ESRD patients on dialysis with permanent AF exhibit elevated MYPT-1 phosphorylation and increased Cx40 expression compared to dialysis patients without AF and healthy controls. These findings align with earlier observations in chronic renal failure and ESRD cohorts [19]. Notably, dialysis patients without AF did not show increased Cx40, indicating that the upregulation of MYPT-1 phosphorylation and Cx40 is specific to the AF subset, with a clear positive correlation between the two markers.
Recent studies using left atrial appendage biopsies from AF patients versus those in sinus rhythm revealed heightened ROCK and MYPT-1 expression, correlating with Cx40 levels—a key gap junction protein facilitating rapid action potential conduction [10]. ROCK, a downstream effector of the RhoA GTPase, is broadly expressed in eukaryotic cells [20]. Activation of RhoA triggers a kinase cascade with diverse biological effects, including NADPH oxidase upregulation and oxidative stress induction. The resultant cardiovascular consequences include altered calcium signaling, reduced nitric oxide bioavailability, conduction disturbances, and impaired contractility [21–24].
Previous work from our group has shown that the ROCK pathway is upregulated in hypertensive patients, evidenced by elevated MYPT-1 phosphorylation and increased levels of p63RhoGEF [9], the latter acting as a specific mediator transmitting the Ang II signal from activated AT1 receptors to RhoA/ROCK signaling [25]. Notably, treatment with the AT1R antagonist olmesartan for six months led to a reduction in RhoA/ROCK activity [26], supporting a central role for this pathway in both the onset and persistence of hypertension [9]. MYPT-1 functions as the catalytic subunit of myosin light chain phosphatase, and its inhibition by ROCK represents a key mechanism driving cardiovascular–renal remodeling [19]. Specifically, ROCK-mediated inhibitory phosphorylation of MYPT-1 enhances myosin light chain kinase activity, promoting structural remodeling of the heart and kidney [9].
Recent studies have reported elevated ROCK activity, as indicated by MYPT-1 phosphorylation, in circulating leukocytes from patients with stable systolic heart failure. In these individuals, ROCK activation was inversely associated with left ventricular (LV) systolic function [27]. Moreover, pharmacological ROCK inhibition has been shown to attenuate cardiac remodeling and improve LV function [28–30], while experimental models of pressure-overload hypertrophy in rats demonstrated that blocking ROCK improves LV geometry, reduces collagen deposition, and enhances diastolic function [28, 31].
In a previous investigation, we observed higher phospho-MYPT-1 levels in CKD and dialysis patients with LV hypertrophy, with MYPT-1 phosphorylation correlating with LV mass [19]. The present study replicates these findings, reinforcing the link between ROCK activity and LV remodeling in this patient population.
The precise mechanistic relationship between the increased MYPT-1 phosphorylation and elevated Cx40 expression observed in our DPAFs remains to be fully elucidated. However, our data indicate that activation of the RhoA/ROCK pathway in dialysis patients with AF coincides with higher Cx40 expression—an essential gap junction protein responsible for rapid intercellular electrical conduction. Furthermore, the positive correlation between MYPT-1 phosphorylation, a marker of ROCK activity, and Cx40 in these patients strengthens the evidence that RhoA/ROCK signaling contributes to AF initiation and maintenance. Supporting this notion, treatment with the ROCK inhibitor Fasudil decreased phospho-MYPT-1 levels and led to a concomitant reduction in Cx40 expression, suggesting that Cx40 may act downstream of RhoA/ROCK activation. Additional mechanistic support could arise from the ERK pathway’s involvement in connexin remodeling, as ERK is a downstream target of MAPK signaling regulated upstream by ROCK [32, 33].
Our inference that observations in circulating mononuclear cells reflect myocardial processes warrants careful consideration. Blood-derived cells are widely used in vascular biology to study ex vivo mechanisms of hypertension and tissue remodeling [34]. Furthermore, the contribution of inflammatory processes, particularly leukocyte infiltration, to hypertensive target organ damage has become increasingly recognized [34]. Evidence also links leukocyte oxidative stress with hypertension [35]. ROCK activity in leukocytes has been shown to promote vascular infiltration and release of proinflammatory cytokines [36], and elevated ROCK activity in peripheral leukocytes has been observed in hypertensive patients [37, 38]. In an animal model, Ocaranza and colleagues demonstrated that ROCK activation in circulating leukocytes mirrors that in myocardial and aortic tissues and is strongly associated with myocardial remodeling [39].
Conclusions
The findings of this study suggest that the ROCK signaling pathway, along with its downstream effector MYPT-1 phosphorylation and Cx40, may play a significant role in the development of atrial fibrillation (AF) in dialysis patients with end-stage renal disease (ESRD), a group particularly vulnerable to cardiovascular complications. Investigating the involvement of the ROCK pathway in AF could offer deeper mechanistic insights into how AF arises in this high-risk population and may reveal new pharmacological targets that could be translated into broader therapeutic strategies for AF management.
Acknowledgments: None.
Conflict of interest: None.
Financial support: None.
Ethics statement: None.