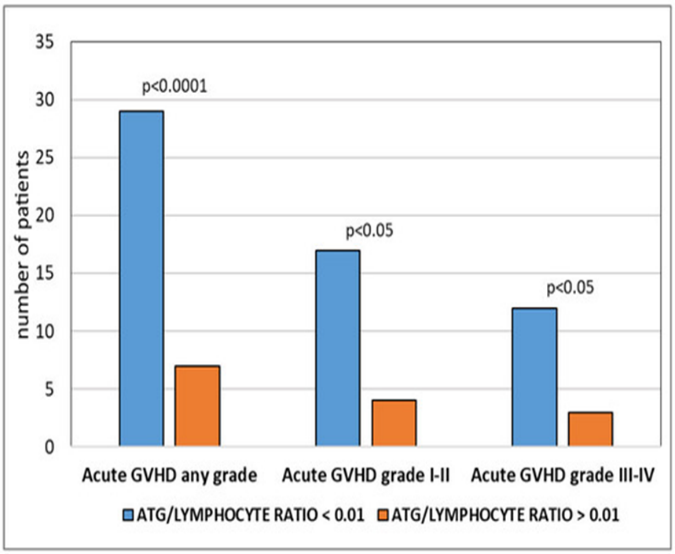
The incorporation of anti-thymocyte globulin (ATG) into conditioning regimens to prevent graft-versus-host disease (GVHD) can markedly impair immune reconstitution (IR). We examined the associations among ATG exposure, recipient lymphocyte counts, IR, and post-transplant outcomes. This retrospective study included patients aged ≤18 years who underwent allogeneic hematopoietic stem cell transplantation (HSCT) from April 2005 to April 2020. Outcomes assessed were GVHD incidence, overall survival (OS), and IR, evaluated via thymic magnetic resonance imaging (MRI) and quantification of CD4+ T cells and recent thymic emigrants (RTEs). Patients receiving ATG were stratified into low (ATG/lymphocyte ratio <0.01) and high (ATG/lymphocyte ratio >0.01) subgroups. The low-ratio group experienced a higher GVHD incidence (29 [59%] vs. 7 [16.6%]) but demonstrated superior IR in both laboratory and MRI assessments (p < 0.0001). Median thymic volume was significantly greater in the low-ratio group (14.7 cm³ vs. 4.5 cm³, p < 0.001), correlating with improved OS and reduced transplant-related mortality (TRM) (80.4% vs. 58.0%, p = 0.031; 13.1% vs. 33.0%, p = 0.035). Tailoring ATG dosing to individual patients may enhance thymic recovery and optimize transplant outcomes.
Introduction
Despite advances in hematopoietic stem cell transplantation (HSCT), graft-versus-host disease (GVHD) continues to pose substantial morbidity and mortality [1, 2]. Immunosuppressive prophylaxis remains the primary strategy to reduce GVHD incidence and severity [3, 4]. While these interventions decrease GVHD-related deaths, relapse and infection-related mortality remain significant contributors to overall survival (OS) in HSCT recipients [5, 6].
The use of anti-thymocyte globulin (ATG) in conditioning regimens has become standard for unrelated or mismatched donor transplants, yet optimal dosing and timing remain unclear, particularly regarding minimizing delays in T-cell reconstitution while maximizing GVHD protection and graft success [7, 8]. Most data derive from adult studies employing high ATG doses due to the higher GVHD burden in adults [9–11]. Standard dosing is weight-based, but patient-specific responses can vary significantly [12–15]. Additionally, the anti-leukemic effects of ATG and its potential impact on relapse rates are not fully understood [16].
Given ATG’s mechanism of T-cell depletion, some studies suggest adjusting its use according to the recipient’s absolute lymphocyte count, as higher pre-transplant lymphocyte levels may reduce ATG’s immunosuppressive effect on donor lymphocytes, potentially increasing GVHD risk [17, 18].
Evidence linking ATG exposure with T-cell reconstitution and transplant outcomes is limited, particularly in pediatric populations, where these relationships are most critical [15, 17, 19, 20]. In this study, we retrospectively assessed pediatric HSCT patients receiving prophylactic ATG, stratifying them based on the ratio of total ATG dose to lymphocyte count on the day of administration.
Successful reconstruction of adaptive immunity post-HSCT relies on thymic activity, as active thymopoiesis is essential for generating a fully functional naïve T-cell pool with broad antigenic diversity [21, 22]. We evaluated thymus-dependent T-cell recovery by measuring thymic volume via MRI and quantifying recent thymic emigrants (RTEs) through immunophenotyping. Finally, we explored potential links between thymic function and transplant outcomes, including GVHD incidence, OS, event-free survival (EFS), and relapse rates.
Materials and Methods
This study was a retrospective analysis conducted at the Pediatric Transplant Center of the Institute for Maternal and Child Health–IRCCS “Burlo Garofolo” in Trieste, Italy. Ethical approval was granted by the IRCCS Burlo Garofolo Institutional Review Board (RC 08/19) and the Unique Regional Ethics Committee (2869), and the study was retrospectively registered on ClinicalTrials.gov (NCT04869254). Written informed consent for research use of clinical data was obtained from all parents.
We reviewed medical records of patients aged 18 years or younger who underwent allogeneic hematopoietic stem cell transplantation (HSCT) between April 2005 and April 2020 and received anti-thymocyte globulin (ATG; Thymoglobulin, Genzyme Europe BV, Amsterdam, The Netherlands) as part of myeloablative conditioning (ATG-exposed group). Only first HSCT procedures were included. No restrictions were placed on transplant indication, cell source, or ATG dose. Patients were excluded if they had received ATG within three months prior to HSCT or had documented ATG hypersensitivity. ATG total doses ranged from 2.5 to 12 mg/kg, reflecting changes in institutional dosing practices over the 15-year period. ATG was usually administered intravenously over three days starting four days before the transplant.
For analysis, the ATG-exposed cohort was divided into two subgroups based on the ratio of total ATG dose (mg) to pre-ATG lymphocyte count (cells × 10²/μL), using 0.01 as the cutoff to balance group sizes.
All patients underwent standard myeloablative conditioning regimens [23]. GVHD prophylaxis included a calcineurin inhibitor and mycophenolate mofetil for matched unrelated donors, with post-transplant cyclophosphamide added from 2013 for haploidentical transplants. Supportive care, including infection prevention and management, followed institutional protocols. Follow-up extended from HSCT until last contact or death, with surviving patients monitored for at least 12 months. Disease risk indices were calculated using refined criteria based on disease type, stage, and cytogenetic risk [24], while thalassemia risk classification followed published guidelines [25]. Ewing sarcoma was considered very high risk when requiring allogeneic transplant.
The primary outcome was GVHD incidence, defined as any episode necessitating systemic immunosuppressive therapy. Acute and chronic GVHD were defined by therapy initiation before or after 100 days post-HSCT, respectively, using standard diagnostic criteria [26, 27]. NIH GVHD scoring could not be applied due to the retrospective design. Secondary endpoints included overall survival (OS), defined as time from HSCT to death from any cause or last follow-up, and relapse-related mortality (RRM), defined as time to death due to disease recurrence. Viral reactivation was recorded if antigen positivity was detected in blood, urine, stool, or surface swabs. Immune reconstitution was defined as recovery of CD4+ T cells to ≥500 cells/μL on two consecutive measurements within 100 days post-HSCT; patients who died before day 100 were analyzed up to death.
Thymic recovery was assessed via MRI at 1, 3, and 12 months post-HSCT, and by quantifying recent thymic emigrants (RTEs) at 100 days and 1 year. RTEs were identified as naïve T cells expressing CD45+CD3+CD4+CD45RA+CD31+ by flow cytometry. For comparison, thymic volumes were obtained from 250 MRI scans of children aged 0–18 years with no hematologic, oncologic, inflammatory, or infectious diseases, stratified by year of age. Additionally, patients undergoing first-time allogeneic HSCT without ATG during the same period were evaluated to compare thymic recovery with controls.
Statistical analysis
Descriptive statistics summarized patient demographics and clinical characteristics. Categorical variables were compared using Fisher’s exact or chi-square tests, while continuous variables were analyzed with the Wilcoxon rank-sum test. Continuous data are reported as medians with interquartile ranges (25th–75th percentiles), and categorical data as counts or percentages. Box-and-whisker plots depicted distributions. The Mann–Whitney test and two-tailed Fisher exact test were applied as appropriate. OS and RRM were estimated using Kaplan–Meier methods and compared by log-rank test. Statistical significance was defined as p < 0.05. Analyses were performed using WinStat v.2012.1 and MedCalc v.18.9.1.
Results and Discussion
Between April 2005 and April 2020, 176 patients underwent HSCT at our center. After applying exclusion criteria, 102 patients were included in the ATG-exposed group and 69 in the ATG-unexposed group. Both groups were comparable in terms of sex distribution, median age at transplant, transplant indication, disease risk index, conditioning regimen, and graft source. Baseline characteristics for both cohorts are summarized in Table 1.
|
Table 1. Baseline patient characteristics and transplant details in ATG-exposed and ATG-unexposed groups |
|||
|
Characteristic |
p-Value |
ATG-Unexposed Group (n = 69) |
ATG-Exposed Group (n = 102) |
|
Sex, n (%) |
|
|
|
|
Male |
0.97 |
42 (60.9) |
60 (58.9) |
|
Female |
0.98 |
27 (39.1) |
42 (41.1) |
|
Age at transplant, years, mean ± SD |
0.86 |
9.03 ± 5.8 |
8.25 ± 5.32 |
|
Underlying disease, n (%) |
|
|
|
|
Acute lymphoblastic leukemia |
0.87 |
25 (36.2) |
39 (38.2) |
|
Acute myeloid leukemia |
0.81 |
14 (20.3) |
19 (18.6) |
|
Myelodysplastic syndrome |
0.63 |
13 (18.8) |
16 (15.6) |
|
Solid tumors |
0.62 |
2 (2.9) |
5 (4.9) |
|
Nonmalignant disorders |
1.00 |
15 (21.7) |
23 (22.5) |
|
Disease risk index, n (%) |
|
|
|
|
Low |
0.84 |
18 (26.1) |
25 (24.5) |
|
Intermediate |
1.00 |
22 (31.9) |
33 (32.4) |
|
High |
1.00 |
19 (27.5) |
28 (27.4) |
|
Very high |
0.79 |
10 (14.5) |
16 (15.7) |
|
Conditioning regimen, n (%) |
|
|
|
|
Myeloablative chemotherapy-based (MCHT) |
0.80 |
44 (63.8) |
70 (68.6) |
|
Total body irradiation-based (TBI) |
0.66 |
25 (36.2) |
32 (31.4) |
|
Graft source, n (%) |
|
|
|
|
Bone marrow |
0.95 |
52 (75.4) |
78 (76.5) |
|
Peripheral blood stem cells |
0.81 |
13 (18.8) |
18 (17.6) |
|
Umbilical cord blood |
1.00 |
4 (5.8) |
6 (5.9) |
|
Donor type, n (%) |
|
|
|
|
Matched related donor |
<0.001 |
69 (100) |
6 (5.9) |
|
Matched unrelated donor |
– |
– |
71 (69.6) |
|
Haploidentical donor |
– |
– |
25 (24.5) |
|
Follow-up, weeks, median (range) |
0.24 |
120 (4–703) |
113 (2–679) |
To assess the impact of ATG exposure on transplant outcomes, the ATG-exposed cohort was further divided into two subgroups based on the ATG/lymphocyte ratio: a low-ratio subgroup (<0.01) and a high-ratio subgroup (>0.01). This stratification was guided by recent studies highlighting the significance of both the recipient’s lymphocyte count at the initiation of ATG infusion and the total cumulative ATG dose [28, 29]. Both subgroups were well-matched with respect to sex, age at transplantation, and disease risk index (Table 2).
|
Table 2. Comparison of transplant outcomes between low ATG/lymphocyte ratio group and high ATG/lymphocyte ratio group |
|||
|
Variables |
p-Value |
ATG/Lymphocyte Ratio > 0.01 (n = 51) |
ATG/Lymphocyte Ratio < 0.01 (n = 51) |
|
Disease risk index, n (%): |
|
|
|
|
Low/Intermediate |
0.59 |
31 (60.8) |
27 (53.0) |
|
High/Very high |
0.54 |
20 (39.2) |
24 (47.0) |
|
Total ATG dose, mg/kg, n (%): |
|
|
|
|
<5 |
0.578 |
15 (57.7) |
11 (42.3) |
|
5–10 |
0.9 |
18 (51.4) |
17 (48.6) |
|
>10 |
0.58 |
18 (43.9) |
23 (56.1) |
|
Lymphocyte count prior to ATG, ×10²/μL, mean ± SD |
<0.001 |
1.49 ± 1.3 |
16.04 ± 13.2 |
|
Mean total ATG dose, mg/kg ± SD |
<0.001 |
13.2 ± 7.3 |
6 ± 3.8 |
|
CD4 count at day +100, cells/μL, mean ± SD |
0.0018 |
127 ± 97 |
330 ± 187 |
|
Time to CD4 > 500 cells/μL, days, median (range) |
0.0431 |
199 (0*–450) |
130 (0*–1095) |
|
Recent thymic emigrants at 1 year, cells/μL, median (range) |
<0.001 |
59 (0*–647) |
206 (0*–924) |
|
Thymic volume at 1 year, cm³, median (range) |
<0.001 |
4.5 (0.2–31.4) |
14.7 (0.4–45.7) |
|
Acute GVHD (any grade), n (%) |
<0.001 |
7 (16.6) |
29 (59.0) |
|
Grade I–II |
<0.001 |
4 (9.5) |
17 (34.4) |
|
Grade III–IV |
<0.05 |
3 (7.1) |
12 (24.5) |
|
Chronic GVHD, n (%) |
0.0965 |
2 (4.8) |
9 (18.4) |
|
Viral infection/reactivation, n (%) |
0.06 |
38 (74.0) |
28 (56.0) |
|
CMV |
0.0437 |
31 (60.7) |
20 (39.2) |
|
EBV |
0.34 |
14 (27.5) |
9 (17.6) |
|
Adenovirus |
1 |
5 (9.8) |
5 (9.8) |
|
<3 episodes |
1 |
14 (27.0) |
14 (27.0) |
|
3–5 episodes |
0.35 |
15 (29.4) |
10 (19.6) |
|
>5 episodes |
0.38 |
9 (17.6) |
5 (8.8) |
|
Endothelial complications, n (%) |
0.12 |
9 (17.6) |
3 (5.9) |
|
Off immunosuppression at 1 year, n (%) |
<0.001 |
32 (91.0) |
26 (63.0) |
|
Overall survival, n (%) |
0.0313 |
30 (58.0) |
41 (80.4) |
|
Event-free survival, n (%) |
0.11 |
24 (47.0) |
33 (64.0) |
|
Non-relapse mortality, n (%) |
0.0357 |
17 (33.0) |
7 (13.1) |
|
GVHD |
– |
1 (2.0) |
0 |
|
VOD |
0.6 |
3 (5.9) |
1 (2.0) |
|
Infection |
0.2 |
8 (15.6) |
3 (5.9) |
|
Other |
0.7 |
5 (9.8) |
3 (5.9) |
|
Relapse-related mortality, n (%) |
0.7 |
5 (9.8) |
3 (5.9) |
Abbreviations: ATG, anti-thymocyte globulin; SD, standard deviation; GVHD, graft-versus-host disease; VOD, veno-occlusive disease; CMV, cytomegalovirus; EBV, Epstein–Barr virus.
*Patients deceased prior to lymphocyte recovery.
**Endothelial complications include VOD, capillary leak syndrome, engraftment syndrome, transplant-associated thrombotic microangiopathies, and diffuse alveolar hemorrhage.
Patients in the subgroup with an ATG/lymphocyte ratio below 0.01 exhibited a markedly higher lymphocyte count before ATG administration and received a considerably lower cumulative ATG dose compared with those in the subgroup with a ratio above 0.01 (p < 0.001; (Table 2)).
GVHD incidence
Acute GVHD developed in 36 patients within the ATG-exposed cohort, comprising 29 individuals (59%) in the low-ratio group and 7 individuals (16.6%) in the high-ratio group (p < 0.001). Within 100 days post-transplant, the cumulative incidence of grade I–II acute GVHD was 34.4 percent in the low-ratio subgroup compared to 9.5% in the high-ratio subgroup (p < 0.001), whereas grade III–IV acute GVHD was observed in 24.5% versus 7.1 percent, respectively (p < 0.05; (Figure 1)). The occurrence of chronic GVHD, either limited or extensive, did not differ significantly between 2 subgroups (p = 0.096).
|
|
|
Figure 1. Cumulative incidence of acute GVHD and its distribution by grade in patients with low ATG/lymphocyte ratio (blue bars) versus high ATG/lymphocyte ratio (orange bars). |
Survival and relapse
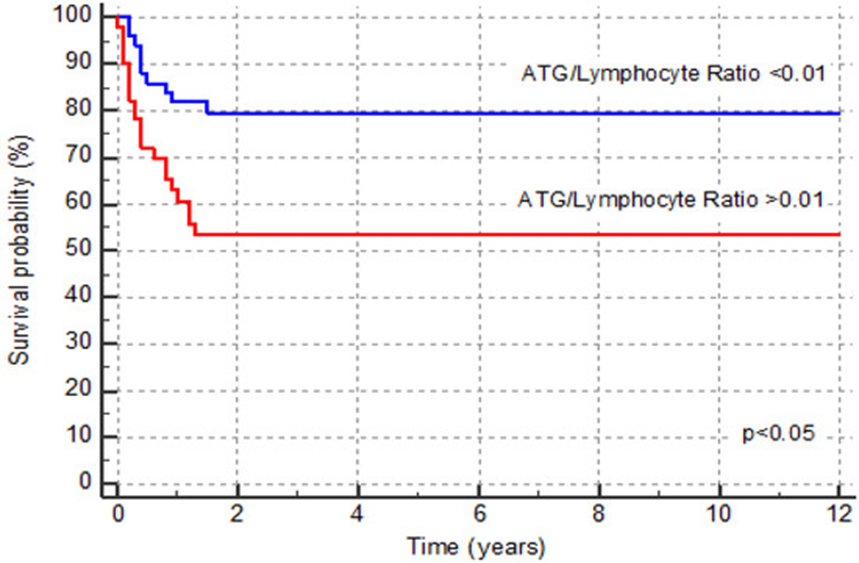
Overall survival was significantly better in the low-ratio subgroup compared with the high-ratio subgroup (80.4 percent vs. 58.0 percent, p = 0.031), whereas non-relapse mortality was notably higher in patients with a high ATG/lymphocyte ratio (33.0% vs. 13.1%, p = 0.035). No statistically significant differences were observed for event-free survival (64% vs. 47%, p = 0.11) or relapse-related mortality (5.9% vs. 9.8%, p = 0.7) between 2 groups. Detailed outcomes, including the specific causes of death in each subgroup, are summarized in Table 2. The OS curves for both subgroups are illustrated in Figure 2. Multivariate Cox regression analysis supported the univariate findings, indicating that primary diagnosis, conditioning regimen, and stem cell source did not significantly influence OS, and that only the ATG/lymphocyte ratio remained an independent predictor of survival (p < 0.03, HR = 2.4, 95 percent CI 1–5.4; (Table 3)).
|
|
|
Figure 2. Kaplan–Meier survival curves illustrating overall survival in patients with a low ATG/lymphocyte ratio (blue line) versus those with a high ATG/lymphocyte ratio (red line). |
|
Table 3. Multivariate Cox proportional hazards analysis for overall survival |
||
|
Variable |
p-Value |
Hazard Ratio (95% CI) |
|
ATG/Lymphocyte ratio |
|
|
|
< 0.01 (Low) |
– |
1 |
|
> 0.01 (High) |
0.03 |
2.4 (1–5.4) |
|
Diagnosis |
|
|
|
LLA |
– |
1 |
|
AML/MDS |
0.06 |
0.32 (0.08–1) |
|
Solid tumor |
0.81 |
1.19 (0.2–5.4) |
|
Non-oncological disease |
0.22 |
0.46 (0.13–1.6) |
|
Conditioning regimen |
|
|
|
TBI-based |
– |
1 |
|
Chemotherapy-based |
0.87 |
1.18 (0.67–3) |
|
Stem cell source |
|
|
|
Bone marrow (BM) |
– |
1 |
|
Peripheral blood stem cells (PBSC) |
0.55 |
0.81 (0.27–2.3) |
|
Cord blood (CB) |
0.46 |
0.46 (0.06–3.6) |
|
Donor type |
|
|
|
Matched unrelated donor (MUD) |
– |
1 |
|
Haploidentical |
0.3 |
1.2 |
Abbreviations: HR, hazard ratio; CI, confidence interval; ATG, anti-thymocyte globulin; AML/MDS, acute myeloid leukemia/myelodysplastic syndrome; TBI, total body irradiation; PBSC, peripheral blood stem cells.
Hematopoietic recovery and viral reactivation
No significant differences were observed in hematopoietic recovery between the two subgroups. Median neutrophil engraftment occurred at 16 ± 5.6 days in the low-ratio subgroup versus 15 ± 6.0 days in the high-ratio subgroup (p = 0.23), while median platelet engraftment was 23 ± 7.9 days versus 25 ± 6.1 days, respectively (p = 0.19).
The cumulative incidence of viral reactivations—including cytomegalovirus (CMV), Epstein–Barr virus (EBV), and adenovirus—was compared between the subgroups (Table 2). Overall, there was no statistically significant difference in viral reactivation rates (p = 0.06) or in the frequency of reactivation episodes. The only exception was CMV, which occurred more frequently in the high-ratio subgroup (60.7%) compared to the low-ratio subgroup (39.2%, p = 0.043).
T-cell recovery and thymic volume post-HSCT
To account for differences in immune recovery, the duration of post-transplant immunosuppression was compared. A significantly greater proportion of patients in the high-ratio subgroup were off immunosuppression at one year post-transplant (91% vs. 63% in the low-ratio subgroup; p < 0.001).
The ATG/lymphocyte ratio during conditioning strongly predicted CD4+ T-cell reconstitution. As shown in Table 2, both thymus-independent and thymus-dependent T-cell recovery were superior in the low-ratio subgroup. CD4+ counts at day +100 were significantly higher in the low-ratio subgroup (p = 0.0018), and these patients reached CD4+ > 500 cells/μL more rapidly (median 130 days vs. 199 days, p = 0.043).
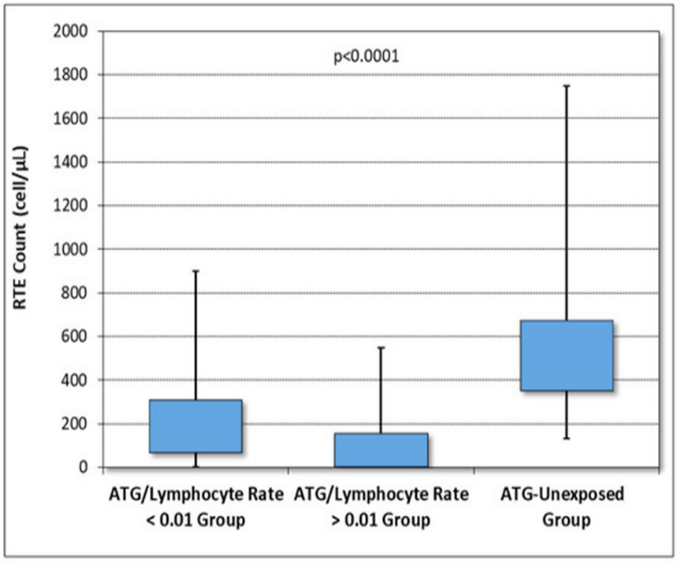
Similarly, the count of recent thymic emigrants (RTEs) at one year post-HSCT was significantly greater in the low-ratio subgroup compared with the high-ratio subgroup (p < 0.001). Comparisons among the low- and high-ratio ATG-exposed groups and the ATG-unexposed cohort (Figure 3) confirmed that thymus-dependent T-cell recovery, measured as RTEs at one year, was markedly superior in patients who had not received ATG (p < 0.0001).
|
|
|
Figure 3. Box-and-whisker plot showing the number of recent thymic emigrants (cells/μL) at one year post-HSCT in the low ATG/lymphocyte ratio group (first box), high ATG/lymphocyte ratio group (second box), and ATG-unexposed group (third box). |
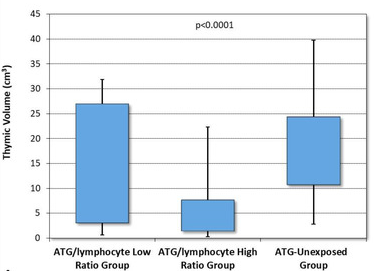
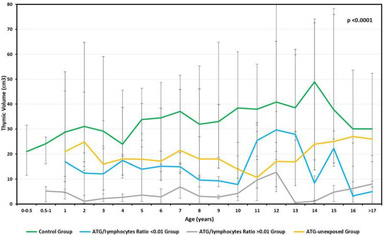
Thymic volume was measured one year after HSCT in both ATG-exposed and ATG-unexposed patients and compared with an age-matched, immunocompetent pediatric control cohort (Figure 4). The median thymic volume was significantly greater in the low-ratio ATG-exposed subgroup than in the high-ratio subgroup (14.7 cm³ vs. 4.5 cm³; p < 0.001; (Table 2)). No significant difference was observed between the low-ratio ATG-exposed subgroup and the ATG-unexposed group (p = 0.082; (Figure 4a)). In addition, thymic volumes in the control group were higher than in both ATG-exposed and ATG-unexposed transplant recipients (p < 0.0001; (Figure 4b)).
|
|
|
a) |
|
|
|
b) |
|
Figure 4. Assessment of thymic volume (cm³) at one year post-HSCT. (a) Comparison of thymic volumes across the low ATG/lymphocyte ratio group (first box), high ATG/lymphocyte ratio group (second box), and ATG-unexposed patients (third box) using a box-and-whisker plot. (b) Age-adjusted thymic volume trends shown as a line graph for the low-ratio group (blue), high-ratio group (grey), ATG-unexposed group (yellow), and the control cohort (green). |
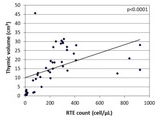
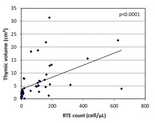
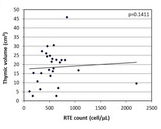
The association between thymic volume and recent thymic emigrant (RTE) counts was evaluated in the two ATG-exposed groups and the ATG-unexposed group at one year post-transplant (Figure 5). A strong positive correlation between thymic size and RTE number was evident in both ATG-exposed subgroups (p < 0.0001; (Figures 5a and 5b)), whereas no statistically significant relationship was observed in the ATG-unexposed cohort (p = 0.1411; (Figure 5c)).
|
|
|
a) |
|
|
|
b) |
|
|
|
c) |
|
Figure 5. Scatter plots illustrating the relationship between thymic volume (cm³) and recent thymic emigrant (RTE) counts (cells/μL) at one year post-HSCT. (a) Correlation in the low ATG/lymphocyte ratio group. (b) Correlation in the high ATG/lymphocyte ratio group. (c) Correlation in the ATG-unexposed group. |
In this retrospective study of pediatric patients, we examined how pre-transplant ATG exposure affects post-HSCT outcomes, focusing on thymic volume recovery and thymus-dependent T-cell reconstitution. Optimizing ATG dosing in children is crucial to balance the prevention of GVHD while minimizing its detrimental effects on immune recovery and infection susceptibility [30, 31].
Our findings suggest that the impact of ATG is not solely determined by the total administered dose but also depends on the recipient’s lymphocyte count at the start of infusion. A high ATG dose combined with a low initial lymphocyte count was associated with poorer overall survival. Correspondingly, T-cell subset recovery and thymic volume restoration were less robust in the high ATG/lymphocyte ratio group compared with the low-ratio group. Previous reports indicate that elevated serum ATG levels, particularly in patients with low lymphocyte counts during the first week post-HSCT, correlate with impaired immune reconstitution and higher infection risk [28, 32]. Unfortunately, serum ATG concentrations were not measured in our cohort, as pharmacokinetic and pharmacodynamic analyses have only recently been implemented at our center.
Existing evidence shows that low lymphocyte counts can only partially bind the administered ATG, leaving free ATG to persist longer in circulation [29]. Our data reinforce prior observations that standard weight-based ATG dosing, without accounting for pre-infusion lymphocyte counts, may result in markedly different circulating ATG levels than when both weight and lymphocyte count are considered [33].
In this study, we evaluated the rates of acute and chronic GVHD in patients with low versus high ATG/lymphocyte ratios. Our findings suggest that higher ATG exposure influences the development of acute GVHD but does not significantly affect chronic GVHD, which contrasts with reports from other studies [10, 34–37] conducted in adult populations, where chronic GVHD incidence is typically higher.
Patients in the low ATG/lymphocyte ratio group demonstrated superior outcomes in overall survival and lower non-relapse mortality, accompanied by reduced rates of bacterial, fungal, opportunistic, and CMV-related infections. These observations align with results from randomized trials and observational studies supporting the safety of moderate ATG exposure regarding infectious complications [8, 38–40].
No significant differences were observed in relapse incidence or relapse-related mortality between the low- and high-ratio subgroups, confirming findings reported in previous literature [41].
A novel aspect of our study was the assessment of ATG exposure on thymic volume restoration and thymopoiesis recovery. Pediatric transplants frequently employ myeloablative conditioning, which can cause prolonged and profound immune suppression, particularly affecting thymopoiesis, sometimes lasting over two years post-transplant [42]. Given the thymus’s central role in T-cell development, optimal thymic recovery is critical for post-HSCT survival [21]. Several factors—including age, acute and chronic GVHD, stem cell source, CMV reactivation, and prior treatment of the underlying hematological malignancy—can impair thymopoiesis recovery [21, 22, 43]. Younger patients generally exhibit more efficient thymic recovery, with the thymus capable of returning to pre-transplant function within one year even after acute GVHD [44, 45].
When comparing thymic volumes among all transplanted patients—both ATG-exposed and unexposed—with healthy age-matched controls, we found that thymic size remained significantly reduced in all transplant recipients, likely due to conditioning-related injury, GVHD, and infection-related complications. Within the transplant cohort, higher ATG exposure was associated with impaired thymic recovery: thymic volumes were significantly smaller in the high ATG/lymphocyte ratio group across all age ranges, whereas no differences were observed between the unexposed and low-ratio groups. Previous studies have demonstrated a dose-dependent cytotoxic effect of rabbit-derived ATG on primary human thymic stromal cells, particularly thymic epithelial cells [46].
Assessment of recent thymic emigrants at one year post-HSCT revealed a significant delay in thymopoiesis in ATG-exposed patients, with the high ATG/lymphocyte ratio subgroup showing the most pronounced impairment. Additionally, we observed a strong correlation between thymic volume and circulating RTE counts in this group, corroborating prior evidence.
Although the retrospective design and heterogeneity of primary diagnoses are limitations, the study is strengthened by the uniformity of myeloablative conditioning, GVHD prophylaxis, and supportive care across patients.
Future research should focus on individualized ATG dosing strategies that preserve post-transplant immune reconstitution while optimizing transplant-related outcomes in pediatric populations.
Acknowledgments: This work was supported by the Ministry of Health, Rome, Italy, in collaboration with the Institute for Maternal and Child Health IRCCS Burlo Garofolo, Trieste, Italy.
Conflict of interest: None
Financial support: None
Ethics statement: The study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Board of the IRCCS Burlo Garofolo (protocol code RC 08/19, 22/03/2019) and Unique Regional Ethics Committee (protocol code 2869, 8 May 2019).
Informed consent was obtained from all subjects involved in the study. Written informed consent has been obtained from the patients to publish this paper.