As transcatheter aortic valve implantation (TAVI) expands to patients with lower surgical risk, reliable prediction of post-procedural outcomes is increasingly critical. Although the effects of gender and atrial fibrillation (AF) on prognosis have been studied individually, their combined influence remains largely unexplored. This retrospective, multicenter study analyzed 1,088 patients who underwent TAVI between May 2010 and February 2020 at three Japanese hospitals. Participants were classified into four groups based on gender and pre-existing AF: Female without AF (n = 559), Male without AF (n = 266), Female with AF (n = 187), and Male with AF (n = 76). The primary outcome was all-cause mortality, while secondary outcomes included cardiovascular death and a composite of mortality and heart failure hospitalization. Over a median follow-up of 538 days, the Female without AF group experienced the lowest rates of adverse events. Multivariate Cox regression demonstrated that both male sex and AF were independently associated with worse outcomes compared to females without AF (reference), with hazard ratios for all-cause death of 2.7 (Male without AF), 3.5 (Female with AF), and 3.9 (Male with AF). However, no additive or synergistic effect between gender and AF was observed. These findings indicate that male gender and AF each independently predict poorer long-term outcomes after TAVI, without amplifying risk when combined.
Introduction
Transcatheter aortic valve implantation (TAVI) has increasingly become a viable alternative to surgical aortic valve replacement (SAVR) for patients with severe aortic stenosis (AS) who are considered high-risk or ineligible for surgery [1, 2]. More recently, clinical trials have demonstrated that TAVI outcomes are comparable to SAVR even in individuals with intermediate or low surgical risk [3–6]. Advances in valve design, procedural techniques, and operator experience have markedly enhanced both safety and early outcomes, leading to broader use of TAVI across the full spectrum of symptomatic severe AS [5, 6].
Given this expansion, identifying patients at risk for adverse long-term outcomes is critical to inform clinical decisions and optimize post-procedural management. Although dedicated TAVI risk scores have been developed [7], conventional cardiac surgery scores—such as the logistic EuroSCORE [8], EuroSCORE II [9], and STS-PROM [10]—remain widely applied in clinical practice.
Among factors influencing prognosis, both patient sex and atrial fibrillation (AF) have emerged as important predictors. Gender-related differences in outcomes following TAVI have been observed since the procedure’s introduction [11], while AF is known to increase mortality and morbidity across populations, including those with AS and TAVI recipients [12, 13]. Despite the recognized interaction between gender and AF in other contexts [14], no studies have yet assessed whether these factors jointly affect outcomes after TAVI. This study aimed to determine whether gender and pre-existing AF interact to influence post-TAVI prognosis, thereby improving risk stratification.
Materials and Methods
Study design and population
This investigation is a retrospective analysis of a prospectively maintained, multicenter TAVI registry comprising patients treated at three Japanese hospitals: Sakakibara Heart Institute, Juntendo University Hospital, and Yamagata University Hospital. The study was conducted in accordance with the Declaration of Helsinki and approved by the Institutional Review Boards of the participating centers (Sakakibara: IRB-ID 17-048; Juntendo: IRB-ID 17-263; Yamagata: IRB-ID 2019-407). The registry is publicly registered with the University Medical Information Network Japan (UMIN000031133), and all participants provided written informed consent.
Patient classification and outcomes
A total of 1,088 patients who underwent TAVI between May 17, 2010, and February 27, 2020, were included. Participants were categorized into four groups based on sex and the presence of AF before the procedure: Female without AF (n = 559, 51.4%), Male without AF (n = 266, 24.4%), Female with AF (n = 187, 17.2%), and Male with AF (n = 76, 7.0%). AF was defined as atrial fibrillation or atrial flutter documented on any pre-TAVI ECG, regardless of ongoing antiarrhythmic or anticoagulant therapy.
The primary outcome was all-cause mortality, including cardiovascular death. Secondary outcomes comprised a composite of all-cause mortality and hospitalization for heart failure. Patients were followed for up to five years, with a median follow-up duration of 538 days.
Statistical analysis
Continuous variables were expressed as mean ± standard deviation or median with interquartile range, depending on data distribution assessed by the Shapiro-Wilk test. Categorical variables were summarized as counts and percentages. Differences across groups were analyzed using ANOVA or the Kruskal-Wallis test for continuous variables and chi-square tests for categorical variables.
Time-to-event analyses were performed using Kaplan-Meier curves with log-rank tests. Cox proportional hazards regression models were applied to evaluate the association of sex, AF, or their combination with outcomes, using the Female without AF group as reference. Multivariate models incorporated clinically relevant covariates identified from baseline characteristics and univariate analyses. Model 1, assessing all-cause mortality, included age, procedure date (pre- or post-2017), BMI, NYHA class, diabetes, COPD, peripheral artery disease, logistic EuroSCORE, hemoglobin, renal function (eGFR), moderate-to-severe mitral or tricuspid regurgitation, valve size, and low-flow low-gradient AS. Model 2, evaluating all-cause and cardiovascular mortality as well as the composite endpoint, included age, NYHA class, prior heart failure, and eGFR. Statistical significance was set at p < 0.05. Analyses were conducted using JMP Pro 12.0 (SAS Institute) and IBM SPSS Statistics 24.0.
Results and Discussion
Patient profiles, comorbidities, and procedural features by sex and af status
Table 1 presents the baseline characteristics, medication use, procedural details, and device information across the four study groups. Male patients without AF were generally younger than their female counterparts, both with and without AF. Comorbidity patterns differed markedly between sexes: men showed higher rates of diabetes, prior stroke, COPD, and previous coronary interventions compared with women.
The presence of AF, irrespective of gender, was linked to a heavier burden of comorbidities. Patients with AF had nearly double the prevalence of prior heart failure, more frequent histories of stroke, and higher rates of chronic kidney disease compared with non-AF patients. These individuals also exhibited elevated NT-proBNP levels, worse NYHA functional class, and reduced kidney function as reflected by lower eGFR values. Across the four groups, prior stroke was most common in Male AF (+) patients, followed sequentially by Female AF (+), Male AF (–), and Female AF (–).
Left ventricular systolic function, measured by ejection fraction, was lowest in the Male AF (+) group and highest in Female AF (–) patients. Interestingly, the pattern of pre-procedural aortic valve gradients mirrored that of LVEF, indicating a higher prevalence of low-gradient AS among male patients with AF. Despite these differences in baseline cardiac and comorbidity profiles, procedural variables—including procedure duration, contrast volume, access route, type of anesthesia, and choice of transcatheter heart valve (balloon- versus self-expanding)—were consistent across all groups.
|
Table 1. Baseline and procedural characteristics of study patients categorized by gender and AF |
||||||
|
Characteristic |
Total Cohort (n = 1088) |
Female, No AF (n = 559, 51.4%) |
Male, No AF (n = 266, 24.4%) |
Female, With AF (n = 187, 17.2%) |
Male, With AF (n = 76, 7.0%) |
p-Value |
|
Age (years) |
84.0 ± 5.5 |
84.1 ± 5.2 |
83.0 ± 6.4 |
85.2 ± 4.9 |
84.2 ± 5.8 |
< 0.001 |
|
Body Mass Index (kg/m²) |
22.3 ± 3.7 |
22.4 ± 3.9 |
22.4 ± 3.0 |
22.1 ± 4.3 |
22.4 ± 3.1 |
0.78 |
|
NYHA Class III/IV (n, %) |
561 (51.7%) |
270 (48.3%) |
133 (50.0%) |
112 (59.9%) |
46 (60.5%) |
0.018 |
|
Logistic EuroSCORE (%) |
12.8 (9.5, 19.0) |
12.8 (9.5, 17.7) |
11.4 (7.6, 19.3) |
16.1 (12.0, 22.4) |
13.6 (8.7, 26.1) |
< 0.001 |
|
EuroSCORE II (%) |
4.5 (2.8, 7.0) |
4.5 (2.8, 6.3) |
3.5 (2.3, 6.5) |
5.3 (3.5, 8.5) |
5.6 (2.5, 10.0) |
< 0.001 |
|
STS-PROM Score (%) |
5.7 (3.8, 8.3) |
5.6 (3.9, 7.7) |
4.9 (3.3, 7.3) |
7.2 (5.4, 10.3) |
6.0 (3.7, 9.3) |
< 0.001 |
|
Comorbidities |
||||||
|
Prior Heart Failure (n, %) |
320 (29.4%) |
132 (23.6%) |
65 (24.4%) |
85 (45.5%) |
38 (50.0%) |
< 0.001 |
|
Hypertension (n, %) |
841 (77.3%) |
445 (79.6%) |
201 (75.6%) |
140 (74.9%) |
55 (72.4%) |
0.28 |
|
Diabetes Mellitus (n, %) |
262 (24.1%) |
117 (20.9%) |
83 (31.2%) |
41 (21.9%) |
21 (27.6%) |
0.0097 |
|
Cancer History (n, %) |
207 (19.0%) |
96 (17.2%) |
59 (22.2%) |
36 (19.3%) |
16 (21.1%) |
0.37 |
|
Prior Stroke (n, %) |
124 (11.4%) |
49 (8.8%) |
35 (13.2%) |
26 (13.9%) |
14 (18.4%) |
0.023 |
|
COPD (n, %) |
112 (10.4%) |
41 (7.4%) |
41 (15.6%) |
22 (11.9%) |
8 (10.5%) |
0.0037 |
|
CKD (Stage ≥ 3) (n, %) |
713 (65.5%) |
353 (63.2%) |
160 (60.2%) |
144 (77.0%) |
56 (73.7%) |
< 0.001 |
|
Peripheral Artery Disease (n, %) |
179 (16.5%) |
75 (13.4%) |
53 (19.9%) |
37 (19.8%) |
14 (18.4%) |
0.052 |
|
Prior Myocardial Infarction (n, %) |
65 (6.0%) |
20 (3.6%) |
31 (11.7%) |
4 (2.1%) |
10 (13.2%) |
< 0.001 |
|
Prior Coronary Revascularization (n, %) |
240 (22.1%) |
94 (16.8%) |
97 (36.5%) |
28 (15.0%) |
21 (27.6%) |
< 0.001 |
|
Prior PTAV (n, %) |
35 (3.2%) |
20 (3.6%) |
6 (2.3%) |
9 (4.8%) |
0 (0.0%) |
0.17 |
|
Laboratory Data |
||||||
|
NT-proBNP (pg/mL) |
1154 (479, 3098) |
868 (386, 2510) |
1025 (409, 2563) |
2173 (1111, 5141) |
1784 (951, 5114) |
< 0.001 |
|
Creatinine (mg/dL) |
0.9 ± 0.4 |
0.8 ± 0.3 |
1.1 ± 0.5 |
0.9 ± 0.4 |
1.1 ± 0.3 |
< 0.001 |
|
eGFR (mL/min) |
54.2 ± 18.9 |
55.4 ± 19.0 |
56.0 ± 19.4 |
49.3 ± 18.3 |
50.8 ± 15.6 |
< 0.001 |
|
Hemoglobin (g/dL) |
11.6 ± 1.6 |
11.3 ± 1.4 |
12.1 ± 1.6 |
11.4 ± 1.5 |
12.1 ± 1.8 |
< 0.001 |
|
Albumin (g/dL) |
3.7 ± 0.4 |
3.8 ± 0.4 |
3.7 ± 0.4 |
3.7 ± 0.4 |
3.7 ± 0.5 |
0.018 |
|
Echocardiographic Findings |
||||||
|
LVEF (%) |
60.7 ± 10.8 |
62.6 ± 9.7 |
58.8 ± 11.6 |
59.8 ± 10.5 |
55.0 ± 13.1 |
< 0.001 |
|
Aortic Valve Area (cm²) |
0.66 ± 0.17 |
0.66 ± 0.17 |
0.70 ± 0.16 |
0.62 ± 0.18 |
0.68 ± 0.20 |
< 0.001 |
|
Peak Gradient (mmHg) |
89.2 ± 31.5 |
92.2 ± 31.3 |
89.0 ± 30.2 |
85.5 ± 33.0 |
77.0 ± 29.8 |
< 0.001 |
|
Mean Gradient (mmHg) |
51.2 ± 19.1 |
53.0 ± 19.6 |
51.0 ± 16.8 |
48.8 ± 20.3 |
43.8 ± 17.9 |
< 0.001 |
|
Aortic Regurgitation ≥ Moderate (n, %) |
56 (5.1%) |
18 (3.2%) |
20 (7.5%) |
12 (6.4%) |
6 (7.9%) |
0.029 |
|
Mitral Regurgitation ≥ Moderate (n, %) |
57 (5.2%) |
21 (3.8%) |
11 (4.1%) |
18 (9.6%) |
7 (9.2%) |
0.0045 |
|
Tricuspid Regurgitation ≥ Moderate (n, %) |
57 (5.2%) |
8 (1.4%) |
5 (1.9%) |
33 (17.6%) |
11 (14.5%) |
< 0.001 |
|
Medications |
||||||
|
Beta-Blockers (n, %) |
382 (35.1%) |
160 (28.6%) |
81 (30.5%) |
99 (52.9%) |
42 (55.3%) |
< 0.001 |
|
ACE Inhibitors/ARBs (n, %) |
596 (54.8%) |
320 (57.3%) |
140 (52.6%) |
90 (48.1%) |
46 (60.5%) |
0.11 |
|
Statins (n, %) |
571 (52.5%) |
286 (51.2%) |
149 (56.0%) |
94 (50.3%) |
42 (55.3%) |
0.48 |
|
Diuretics (n, %) |
516 (47.4%) |
227 (40.6%) |
115 (43.2%) |
117 (62.6%) |
57 (75.0%) |
< 0.001 |
|
Oral Anticoagulants (n, %) |
261 (24.0%) |
27 (4.8%) |
15 (5.6%) |
162 (86.6%) |
57 (75.0%) |
< 0.001 |
|
Procedural Variables |
||||||
|
Procedure Duration (min) |
73 (60, 100) |
74 (60, 102) |
73 (60, 97) |
72 (59, 100) |
73 (58, 101) |
0.95 |
|
Fluoroscopy Duration (min) |
20 (16, 27) |
21 (16, 27) |
20 (16, 27) |
20 (16, 26) |
20 (17, 28) |
0.88 |
|
Contrast Volume (mL) |
61 (45, 96) |
63 (46, 98) |
60 (45, 94) |
61 (43, 95) |
55 (42, 86) |
0.30 |
|
Approach Plan |
||||||
|
Conscious Sedation (n, %) |
637 (58.6%) |
336 (60.1%) |
157 (59.0%) |
101 (54.0%) |
43 (56.6%) |
0.51 |
|
Transfemoral Approach (n, %) |
993 (91.3%) |
517 (92.5%) |
242 (91.0%) |
166 (88.8%) |
68 (89.5%) |
0.58 |
|
Valve Size (mm) |
24.8 ± 2.3 |
24.1 ± 2.1 |
26.1 ± 2.3 |
24.2 ± 2.1 |
26.2 ± 2.3 |
< 0.001 |
|
Valve Type |
||||||
|
Edwards SAPIEN-XT (n, %) |
171 (15.7%) |
92 (16.5%) |
33 (12.4%) |
32 (17.1%) |
14 (18.4%) |
0.38 |
|
Edwards SAPIEN3 (n, %) |
543 (49.9%) |
275 (49.2%) |
150 (56.4%) |
84 (44.9%) |
34 (44.7%) |
0.052 |
|
Medtronic CoreValve (n, %) |
29 (2.7%) |
14 (2.5%) |
11 (4.1%) |
3 (1.6%) |
1 (1.3%) |
0.30 |
|
Medtronic Evolut R (n, %) |
164 (15.1%) |
88 (15.7%) |
27 (10.2%) |
40 (21.4%) |
9 (11.8%) |
0.0072 |
|
Medtronic Evolut PRO (n, %) |
128 (11.8%) |
66 (11.8%) |
30 (11.3%) |
17 (9.1%) |
15 (19.7%) |
0.13 |
|
Boston Scientific LOTUS (n, %) |
11 (1.0%) |
5 (0.9%) |
3 (1.1%) |
2 (1.1%) |
1 (1.3%) |
0.98 |
|
Balloon-Expandable Valve (n, %) |
714 (65.6%) |
367 (65.7%) |
183 (68.8%) |
116 (62.0%) |
48 (63.2%) |
0.45 |
BMI: body mass index, STS-PROM: Society of Thoracic Surgeons Predicted Risk of Mortality, COPD: chronic obstructive pulmonary disease, CKD: chronic kidney disease, PAD: peripheral artery disease, OMI: old myocardial infarction, PTAV: percutaneous transcatheter aortic valvuloplasty, NT-proBNP: N-terminal pro-brain natriuretic peptide, eGFR; estimated glomerular filtration rate, LVEF: left ventricular ejection fraction, AVA: aortic valve area, AR: aortic regurgitation, MR: mitral regurgitation, TR: tricuspid regurgitation, ACEis: angiotensin converting enzyme inhibitors, ARBs: angiotensin II receptor blockers. * status post percutaneous coronary intervention or coronary artery bypass graft. Bold values indicate statistical significance at the p < 0.05 level.
In-Hospital and long-term outcomes after TAVI by gender and AF
Over a median follow-up of 538 days and extending up to five years post-TAVI, there were 141 all-cause deaths (13.0%), 59 cardiovascular (CV) deaths (5.4%), and 183 events comprising the composite of all-cause mortality and heart failure (HF) hospitalization (16.8%) among the 1,088 patients. Most in-hospital complications were comparable across the four groups, with the exception of acute kidney injury, which showed some variation (Supplementary Table S1).
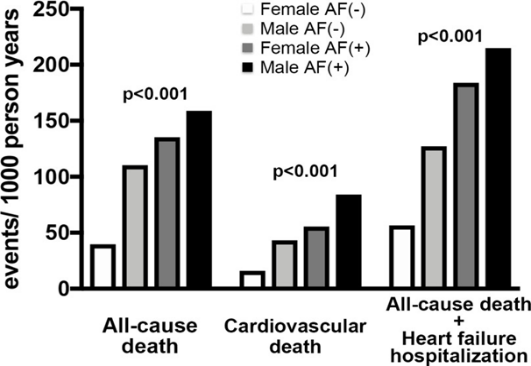
Long-term crude event rates, expressed as events per 1,000 person-years, differed significantly among the groups. Male patients with AF consistently experienced the highest rates of all endpoints, whereas females without AF had the lowest rates. Male patients without AF and females with AF had intermediate event frequencies (Figure 1).
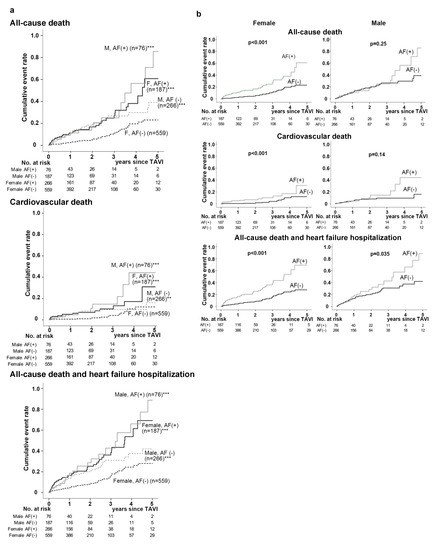
Kaplan-Meier analyses, unadjusted for covariates, further confirmed these trends: the Female AF (–) group consistently demonstrated the lowest cumulative incidence for all endpoints compared with the other three groups (Figure 2a; Supplementary Figure S1a). Notably, higher cumulative rates of all-cause and CV mortality associated with AF were observed primarily in female patients, while the composite endpoint of all-cause death and HF hospitalization was elevated in AF patients of both sexes (Figure 2b).
|
Figure 1. Crude numbers of adverse events following TAVI in the 4 study groups divided according to gender and preprocedural AF. The number per 1000 person years of all-cause and cardiovascular mortalities, and the composite of all-cause death and heart failure hospitalization after TAVI were significantly different among the groups. The order of all events was identical; from the lowest to the highest; Female AF (–), Male AF (-), Female AF (+) and Male AF (+) |
Post-TAVI outcomes by gender and AF
During the five-year period following TAVI, 141 patients (13.0%) died from any cause, 59 (5.4%) died from cardiovascular causes, and 183 (16.8%) experienced the composite endpoint of all-cause mortality or hospitalization for heart failure. Rates of most in-hospital complications were similar across groups, except for acute kidney injury, which showed some variability (Supplementary Table S1). Long-term event rates, expressed per 1,000 person-years, varied notably between the four groups. Patients who were male with AF consistently had the highest occurrence of all endpoints, whereas females without AF experienced the fewest events. Male patients without AF and females with AF had intermediate event frequencies (Figure 1).
Unadjusted Kaplan-Meier curves reinforced these trends, demonstrating that females without AF had the lowest cumulative incidence for all outcomes compared with the other three groups (Figure 2a; Supplementary Figure S1a). Interestingly, the presence of AF was associated with higher cumulative all-cause and cardiovascular mortality primarily among female patients, while the combined endpoint of death and heart failure hospitalization was elevated in AF patients of both sexes (Figure 2b).
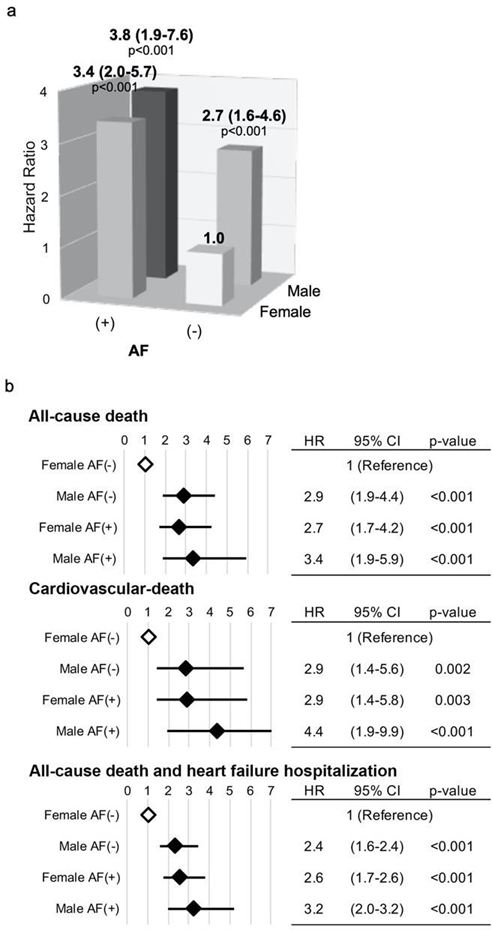
To further explore the combined influence of male sex and AF, multivariate Cox regression analyses were conducted using females without AF as the reference group. Analyses incorporating a comprehensive set of covariates revealed that both male gender and AF independently increased the risk of all-cause mortality, and their coexistence was linked to the highest risk. When a more limited set of covariates was applied to evaluate multiple endpoints, including all-cause and cardiovascular mortality, the composite of death and heart failure hospitalization, and heart failure events alone, results were consistent. Male patients with AF had more than a threefold higher risk of all-cause (HR 3.4) and cardiovascular mortality (HR 4.4) compared with females without AF. For heart failure hospitalization specifically, AF emerged as the predominant risk factor, while gender exerted a smaller influence. These findings indicate that male sex and AF each contribute independently to poorer long-term outcomes after TAVI, with their combination particularly amplifying the risk of mortality.
|
|
|
Figure |
This study examined the combined influence of gender and pre-existing atrial fibrillation (AF) on long-term outcomes after TAVI, evaluating all-cause and cardiovascular mortality as well as the composite of death and heart failure hospitalization across four patient groups defined by sex and AF status. By categorizing patients in this way, potential statistical interactions between AF and gender were avoided, allowing a clearer assessment of their independent effects.
The principal findings of this analysis are as follows. In-hospital mortality and major perioperative complications were comparable across all groups. However, when outcomes were tracked over a five-year period, significant differences emerged. Patients who were female without AF experienced the lowest incidence of adverse events, whereas male patients with AF consistently exhibited the highest rates. Kaplan-Meier analyses confirmed these trends, with females without AF demonstrating the lowest cumulative incidence across all endpoints. Multivariate Cox regression further demonstrated that both male sex and AF independently increased the risk of all adverse outcomes. Notably, the coexistence of male sex and AF did not result in a synergistic elevation of risk, highlighting their independent contributions to long-term prognosis after TAVI.
Aortic valve replacement improves cardiac hemodynamics by reducing afterload in patients with severe AS, and technical refinements in TAVI have progressively reduced perioperative risk [15]. Despite these advances, long-term mortality after TAVI remains substantial [16], emphasizing the need for accurate risk stratification not only for procedural safety but also for long-term outcomes, particularly as TAVI expands to lower-risk populations [5]. Traditional risk scores, such as EuroSCORE, EuroSCORE II, and STS-PROM, remain widely used for short-term risk assessment, but these tools were originally developed for surgical populations and may not reliably predict long-term outcomes in TAVI recipients [17,18]. In prior analyses of this registry, the STS-ACC TAVR risk score, specifically designed for TAVI patients, demonstrated superior predictive performance compared with conventional models [19]. The addition of AF, along with serum albumin and body mass index, further improved the accuracy of risk prediction, underscoring the importance of AF as a prognostic factor in TAVI.
The influence of gender on TAVI outcomes has been inconsistently reported in the literature. Some studies indicate improved mid- to long-term survival in women [20, 21], while others have found comparable or worse outcomes compared with men [22, 23]. Large registry analyses and meta-analyses have suggested higher rates of vascular complications and short-term mortality among women, potentially related to higher utilization of non-transfemoral TAVI approaches [24, 25]. In contrast, the present study observed similar short-term outcomes between men and women, but women experienced significantly better long-term survival. The low proportion of non-transfemoral TAVI (8.7%) in this cohort, together with similar access site distributions across the four groups, likely contributed to the absence of sex-based differences in early outcomes. These observations suggest that procedural factors had a limited effect on long-term prognosis in this study population, highlighting the independent roles of gender and AF in shaping post-TAVI outcomes.
Aortic stenosis (AS) imposes pressure overload on the left atrium, promoting structural remodeling that predisposes patients to atrial fibrillation (AF), which in turn increases the risk of adverse events such as stroke and heart failure [26, 27]. Increasing evidence supports the negative prognostic impact of both pre-existing and new-onset AF in patients undergoing TAVI [28, 29]. In the present study, the overall prevalence of pre-existing AF was 24.3%, aligning with prior reports that ranged between 16% and 51.1% [13]. Contrary to earlier studies reporting higher AF prevalence among men, AF occurred at a similar rate in both sexes in this cohort [25]. Interestingly, the adverse impact of AF on all-cause and cardiovascular mortality was more pronounced in women than in men. While the smaller number of male participants may have limited the statistical power to detect a significant effect, these findings suggest the possibility of a gender-specific influence of AF on post-TAVI prognosis. Given established sex differences in AF epidemiology, clinical presentation, and outcomes [30], it is plausible that male sex and AF could have additive effects on adverse events, although synergistic interactions remain uncertain.
Previous research has typically examined the effects of gender or AF separately on short- and long-term TAVI outcomes, with few studies considering their combined impact. The present analysis demonstrates that both male sex and pre-existing AF independently increased the risk of all-cause and cardiovascular mortality as well as the composite of death and heart failure hospitalization. While patients with both risk factors exhibited the highest hazard ratios for all endpoints, the combined presence of male sex and AF did not result in a statistically significant synergistic increase in risk. These observations suggest a primarily independent, with a minor additive, effect of these factors on post-TAVI outcomes.
Limitations
Several limitations should be noted when interpreting these findings. First, the registry included a relatively small number of institutions and patients, and the retrospective design may allow unmeasured confounding factors to influence outcomes. Second, temporal changes in the prognostic impact of gender and AF should be considered. Previous work has suggested that the survival advantage of female TAVI patients has diminished in more contemporary cohorts [31]. Although the majority of participants in this study (96.3%) were classified as contemporary, and the multivariate model accounted for the year of TAVI, residual temporal effects cannot be excluded. Third, while this study found no significant synergistic effect of male sex and AF in the overall cohort, such an effect cannot be completely ruled out in specific subpopulations. Fourth, similar to other large Japanese TAVI registries [32], females constituted a higher proportion of patients than in many international studies [7, 31, 33], which may have influenced the observed results. Future investigations incorporating data from diverse global registries are needed to validate these findings.
Conclusion
In summary, this retrospective cohort study from a multicenter Japanese registry demonstrates that male sex and pre-existing AF are independently associated with an increased risk of all-cause and cardiovascular mortality, as well as the composite of death and heart failure hospitalization following TAVI. Although no evidence of a synergistic effect between these two factors was observed, their individual prognostic significance underscores the importance of considering both gender and AF in clinical decision-making and post-procedural management. These findings highlight the need for tailored treatment strategies and vigilant follow-up in patients undergoing TAVI to optimize long-term outcomes.
Acknowledgments: The authors wish to thank Morimasa Takayama and Tetsuya Tobaru for their significant contributions to this registry database. The authors also appreciate the statistical assistance of Ryo Naito during the process of preparing the revised version of the manuscript.
Conflict of interest: None.
Financial support: This study was supported by the Sakakibara Clinical Research Grant for Promotion of Sciences, 2020 year. grant number H-4-2020.
Ethics statement: None.